


All patients undergoing long-term kidney replacement therapy (KRT) develop accompanying metabolic and other disorders. These disorders require appropriate attention and adjunctive treatment. Approach varies by patient but typically includes nutritional modifications and management of multiple metabolic abnormalities (see also Nutrition and Overview of Kidney Replacement Therapy).
Nutrition
Diet should be carefully controlled. Generally, patients on hemodialysis tend to be anorexic and should be encouraged to eat a daily diet of 25 to 35 kcal/kg ideal body weight (40 to 90 kcal/kg/day in children and 70 to 120 kcal/kg/day in infants, individualized to age and activity) (1, 2, 3). The recommended protein intake for patients undergoing dialysis is 1.0 to 1.2 g/kg/day. Daily sodium intake should be limited to 2.3 g (100 mEq [100 mmol]). Potassium and phosphorous intake should be adjusted to achieve normal levels. Fluid intake, inclusive of the fluids contained in food, is generally limited to 1000 to 1500 mL/day and monitored by measuring weight gain between dialysis treatments (4).
Survival is best among patients (both hemodialysis and peritoneal dialysis) who are not underweight, based on body mass index, and maintain a serum albumin> 3.5 g/dL (35 g/L); serum albumin is the best predictor of survival in these patients.


Anemia of kidney failure
Anemia is a common complication that occurs in kidney failure, affecting approximately 85% of patients (4), and should be treated with erythropoiesis-stimulating agents (ESAs) and iron supplementation (see Anemia of Renal Disease and Anemia and coagulation disorders). Because the absorption of oral iron is limited in kidney failure, many patients require IV iron. IV iron is specifically recommended over oral iron for patients receiving hemodialysis, where it can be conveniently administered during dialysis sessions (5). Ferric carboxymaltose, sodium ferric gluconate, and iron sucrose are preferred to iron dextran, which has a higher incidence of anaphylaxis.
Initial screening is with a complete blood count, reticulocyte count, and ferritin and iron saturation determinations; additional testing is performed if the cause of anemia is not clearly iron deficiency. For patients receiving hemodialysis who have iron deficiency anemia, iron therapy is recommended if ferritin is ≤ 500 ng/mL (≤ 500 mcg/L) and iron saturation is ≤ 30%. For patients receiving peritoneal dialysis, it is recommended if ferritin is < 100 ng/mL (< 100 mcg/L) if iron saturation is < 40% or ferritin < 300 ng/mL (300 mcg/L) if iron saturation is < 25% (5). Iron stores are assessed before the start of erythropoietin therapy and thereafter every 3 months (for those receiving peritoneal dialysis) or every 1 to 3 months (for those receiving hemodialysis) (5). Iron deficiency is the most common reason for erythropoietin resistance. However, some patients on dialysis who have received multiple blood transfusions have iron overload and should not be given iron supplements.
Cardiovascular disease
Cardiovascular disease is a major cause of morbidity among patients receiving hemodialysis. Atherosclerotic cardiovascular disease (ASCVD) is estimated to be present in 40% adults receiving hemodialysis, and hypertension-related complications such as left ventricular hypertrophy are even more common. In addition, arrhythmias and sudden cardiac death occur at substantially higher rates than in the general population (6, 7).
Risk factors for atherosclerosis must be managed aggressively because many patients who require KRT have hypertension, dyslipidemia, or diabetes or smoke cigarettes. Ultimately cardiovascular disease is the leading cause of death in patients receiving hemodialysis (7, 8). Diabetes management, and smoking cessation are very important. Lipid-lowering therapies, while safe and effective in lowering low-density lipoprotein (LDL) cholesterol, do not reduce atherosclerotic events in patients on dialysis and are thus not routinely recommended (although patients taking statins prior to starting dialysis may continue them) (9, 10).
Hypertension can be controlled in many patients receiving hemodialysis by filtration alone. Antihypertensive medications are required in the remainder.
Implantable cardioverter-defibrillator therapy does not appear to reduce sudden death or overall mortality in patients on dialysis (11, 12).
Hyperphosphatemia
Hyperphosphatemia, a consequence of phosphate retention due to low glomerular filtration rate (GFR), increases risk of soft-tissue calcification, especially in coronary arteries and heart valves. It also stimulates development of secondary hyperparathyroidism. Patients with hyperphosphatemia should avoid foods high in phosphorus (13). Pharmacologic treatment options include calcium-based phosphorus binders, non-calcium–based phosphorus binders, or inhibition of phosphorus absorption.
Calcium-based phosphorus binders include calcium carbonate taken orally 3 times a day with meals, and calcium acetate taken orally 3 times a day with meals. These are less expensive than the other phosphorus binders, but they can cause vascular calcification, as well as hypercalcemia.
Non-calcium–based phosphorus binders include sevelamer, lanthanum carbonate, sucroferric oxyhydroxide, or ferric citrate with each meal. Use of non-calcium–based phosphorus binders is associated with a 22% decrease in all-cause mortality when compared with use of calcium-based phosphorus binders (14). Some patients (eg, those hospitalized with acute kidney injury and very high serum phosphate concentrations) require the addition of aluminum-based phosphate binders, but these should be used as short-term medications only (eg, 1 to 2 weeks as needed) to prevent aluminum toxicity (13).
Tenapanor inhibits phosphorus absorption in the gastrointestinal tract and can be used as add-on therapy for patients with inadequate response to phosphorus binders (15). Diarrhea is a potential adverse effect.
Hypocalcemia and secondary hyperparathyroidism
These complications often coexist as a result of impaired renal production of vitamin D and hypophosphatemia. Treatment of hypocalcemia, which drives secondary hyperparathyroidism, is with calcitriol either orally or IV (13). Treatment can increase serum phosphate level and should be withheld until the level is normalized to avoid soft-tissue calcification. Doses are titrated to suppress parathyroid hormone (PTH) levels, usually to 150 to 600 pg/mL ([150 ng/L to 600 ng/L]; PTH reflects bone turnover better than serum calcium). Oversuppression decreases bone turnover and leads to adynamic bone disease, which carries a high risk of fracture. The vitamin D analogs doxercalciferol and paricalcitol have less effect on calcium and phosphate absorption from the gut but suppress PTH equally well, although the relative effect on mortality is not clear (16, 17). Finally, cinacalcet, a calcimimetic medication, increases sensitivity of parathyroid calcium-sensing receptors to calcium and is another option for treating secondary hyperparathyroidism in patients receiving dialysis.
Parathyroidectomy may be necessary in patients with secondary hyperparathyroidism refractory to medical therapy.
Aluminum toxicity
Toxicity is a risk in hemodialysis patients who are exposed to aluminum-contaminated dialysate (uncommon) and aluminum-based phosphate binders. Manifestations are osteomalacia, microcytic anemia (iron-resistant), and probably dialysis dementia (a constellation of memory loss, dyspraxia, hallucinations, facial grimaces, myoclonus, seizures, and a characteristic electroencephalogram [EEG]).
Aluminum toxicity should be considered in patients receiving KRT who develop osteomalacia, iron-resistant microcytic anemia, or neurologic manifestations such as memory loss, dyspraxia, hallucinations, facial grimaces, myoclonus, or seizures. Diagnosis is by measurement of plasma aluminum before and 2 days after IV infusion of deferoxamine 5 mg/kg (18). Deferoxamine chelates aluminum, releasing it from tissues and increasing the blood level among patients with aluminum toxicity. A rise in aluminum level of ≥ 50 mcg/L suggests toxicity. Aluminum-related osteomalacia can also be diagnosed by needle biopsy of bone (requires special stains for aluminum).
Treatment is avoidance of aluminum-based binders plus IV or intraperitoneal deferoxamine.
Pearls & Pitfalls
|
Bone disease
Renal osteodystrophy is abnormal bone mineralization. It has multiple causes, including vitamin D deficiency, elevated serum phosphate, secondary hyperparathyroidism, chronic metabolic acidosis, and aluminum toxicity. Treatment is of the cause.
Vitamin deficiencies
Vitamin deficiencies result from dialysis-related loss of water-soluble vitamins (eg, B, C, folate) and can be replenished with daily renal multivitamin supplements (eg, containing thiamine, riboflavin, niacin/niacinamide, vitamin B6, vitamin B12, folic acid, and pantothenic acid).
Calciphylaxis
Calciphylaxis is a rare disorder of systemic arterial calcification causing ischemia and necrosis in localized areas of the fat and skin of the trunk, buttocks, and lower extremities. Cause is unknown, though hyperparathyroidism, vitamin D supplementation, and elevated calcium (Ca) and phosphate (PO4) levels are thought to contribute. It manifests as painful, violaceous, purpuric plaques and nodules that ulcerate, form eschars, and become infected. It is often fatal. Treatment is usually supportive. Several cases have been reported in which sodium thiosulfate given IV at the end of dialysis 3 times a week along with aggressive efforts to reduce the serum Ca × PO4 product has resulted in considerable improvement (19, 20). There have been some studies that also suggest that vitamin K supplementation may be beneficial (21).

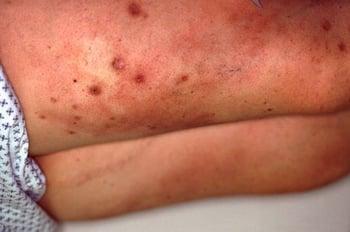
This image shows early skin changes of ischemia and necrosis in localized areas resulting from calciphylaxis.
Constipation
Constipation is a minor but troubling aspect of long-term KRT and, because of resulting bowel distention, may interfere with catheter drainage in peritoneal dialysis. Many patients require osmotic (eg, sorbitol) or bulk (eg, psyllium) laxatives. Laxatives containing magnesium (eg, magnesium hydroxide) or phosphate (eg, sodium phosphate enema) should be avoided.
References
1. Ikizler TA, Burrowes JD, Byham-Gray LD, et al. KDOQI Clinical Practice Guideline for Nutrition in CKD: 2020 Update. Am J Kidney Dis. 2020;76(3 Suppl 1):S1-S107. doi:10.1053/j.ajkd.2020.05.006
2. KDOQI Work Group. KDOQI Clinical Practice Guideline for Nutrition in Children with CKD: 2008 update. Executive summary. Am J Kidney Dis. 2009;53(3 Suppl 2):S11-S104. doi:10.1053/j.ajkd.2008.11.017
3. Polderman N, Shaw V, Anderson CE, et al. Ten tips on how to optimize nutrition in children with chronic kidney disease or on dialysis. Clin Kidney J. 2026;19(4):sfag046. Published 2026 Feb 12. doi:10.1093/ckj/sfag046
4. Flythe JE, Watnick S. Dialysis for Chronic Kidney Failure: A Review. JAMA. 2024;332(18):1559-1573. doi:10.1001/jama.2024.16338
5. Kidney Disease: Improving Global Outcomes (KDIGO) Anemia Work Group. KDIGO 2026 Clinical Practice Guideline for the Management of Anemia in Chronic Kidney Disease (CKD). Kidney Int. 2026;109(1S):S1-S99. doi:10.1016/j.kint.2025.06.006
6. Cozzolino M, Mangano M, Stucchi A, Ciceri P, Conte F, Galassi A. Cardiovascular disease in dialysis patients. Nephrol Dial Transplant. 2018;33(suppl_3):iii28-iii34. doi:10.1093/ndt/gfy174
7. Sarnak MJ, Auguste BL, Brown E, et al. Cardiovascular Effects of Home Dialysis Therapies: A Scientific Statement From the American Heart Association. Circulation. 2022;146(11):e146-e164. doi:10.1161/CIR.0000000000001088
8. U.S. Renal Data System (USRDS), National Institute of Diabetes and Digestive and Kidney Diseases. End Stage Renal Disease. Accessed May 28, 2026.
9. Blumenthal RS, Morris PB, Gaudino M, et al. 2026 ACC/AHA/AACVPR/ABC/ACPM/ADA/AGS/APhA/ASPC/NLA/PCNA Guideline on the Management of Dyslipidemia: A Report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines. J Am Coll Cardiol. 2026;87(19):2624-2757. doi:10.1016/j.jacc.2025.11.016
10. Ferro CJ, Mark PB, Kanbay M, et al. Lipid management in patients with chronic kidney disease. Nat Rev Nephrol. 2018;14(12):727-749. doi:10.1038/s41581-018-0072-9
11. Jukema JW, Timal RJ, Rotmans JI, et al. Prophylactic Use of Implantable Cardioverter-Defibrillators in the Prevention of Sudden Cardiac Death in Dialysis Patients. Circulation. 2019;139(23):2628-2638. doi:10.1161/CIRCULATIONAHA.119.039818
12. Russo AM, Desai MY, Do MM, et al. ACC/AHA/ASE/HFSA/HRS/SCAI/SCCT/SCMR 2025 Appropriate Use Criteria for Implantable Cardioverter-Defibrillators, Cardiac Resynchronization Therapy, and Pacing. J Am Coll Cardiol. 2025;85(11):1213-1285. doi:10.1016/j.jacc.2024.11.023
13. Kidney Disease: Improving Global Outcomes (KDIGO) CKD-MBD Update Work Group. KDIGO 2017 clinical practice guideline update for the diagnosis, evaluation, prevention, and treatment of chronic kidney disease—Mineral and bone disorder (CKD-MBD). Kidney Int Suppl (2011). 2017;7(1):1-59. doi:10.1016/j.kisu.2017.04.001
14. Jamal SA, Vandermeer B, Raggi P, et al. Effect of calcium-based versus non-calcium-based phosphate binders on mortality in patients with chronic kidney disease: an updated systematic review and meta-analysis. Lancet. 2013;382(9900):1268-1277. doi: 10.1016/S0140-6736(13)60897-1
15. Pergola PE, Rosenbaum DP, Yang Y, et al. A randomized trial of tenapanor and phosphate binders as a dual-mechanism treatment for hyperphosphatemia in patients on maintenance dialysis (AMPLIFY). J Am Soc Nephrol. 2021;32(6):1465-1473. doi: 10.1681/ASN.2020101398
16. Palmer SC, McGregor DO, Craig JC, Elder G, Macaskill P, Strippoli GF. Vitamin D compounds for people with chronic kidney disease requiring dialysis. Cochrane Database Syst Rev. 2009;(4):CD005633. doi:10.1002/14651858.CD005633.pub2
17. Xie Y, Su P, Sun Y, et al. Comparative efficacy and safety of paricalcitol versus vitamin D receptor activators for dialysis patients with secondary hyperparathyroidism: a meta-analysis of randomized controlled trials. BMC Nephrol. 2017;18(1):272. doi:10.1186/s12882-017-0691-6
18. Barata JD, D'Haese PC, Pires C, Lamberts LV, Simões J, De Broe ME. Low-dose (5 mg/kg) desferrioxamine treatment in acutely aluminium-intoxicated haemodialysis patients using two drug administration schedules. Nephrol Dial Transplant. 1996;11(1):125-132.
19. Zitt E, König M, Vychytil A, et al. Use of sodium thiosulphate in a multi-interventional setting for the treatment of calciphylaxis in dialysis patients. Nephrol Dial Transplant. 2013;28(5):1232-1240. https://doi.org/10.1093/ndt/gfs548
20. Nigwekar SU, Brunelli SM, Meade D, et al. Sodium thiosulfate therapy for calcific uremic arteriolopathy. Clin J Am Soc Nephrol. 2013;8(7):1162-1170. doi:10.2215/CJN.09880912
21. Nigwekar SU. Phase 2 trial of phytonadione in calciphylaxis. American Society of Nephrology. Abstract TH-PO1188. Accessed May 28, 2026.
Drug Information for the Topic




