


Acne vulgaris is the formation of comedones, papules, pustules, nodules, and/or cysts as a result of obstruction and inflammation of pilosebaceous units (hair follicles and their accompanying sebaceous gland). Acne develops on the face and upper trunk. It most often affects adolescents. Diagnosis is by examination. Treatment, based on severity, can involve a variety of topical and systemic agents directed at reducing sebum production, comedone formation, inflammation, and bacterial counts and at normalizing keratinization.
Acne vulgaris is a common chronic inflammatory skin disease of the pilosebaceous unit. Clinical manifestations of acne are highly variable and depend on disease severity. Acne is a prevalent skin condition. A global population-based analysis of the Global Burden of Disease data reported an age-standardized prevalence rate of acne vulgaris of 30.7 per 1000 people (1). The incidence of acne appears to be increasing over time. There is a female preponderance.
Acne most commonly affects adolescents and young adults, but it also frequently occurs in adults. A cross-sectional survey study found that among adults in their 40s, 26% of women and 12% of men reported having acne (2).
General references
1. Chen H, Zhang TC, Yin XL, et al. Magnitude and temporal trend of acne vulgaris burden in 204 countries and territories from 1990 to 2019: an analysis from the Global Burden of Disease Study 2019. Br J Dermatol. 2022;186(4):673-683. doi:10.1111/bjd.20882
2. Collier CN, Harper JC, Cafardi JA, et al. The prevalence of acne in adults 20 years and older. J Am Acad Dermatol. 2008;58(1):56-59. doi: 10.1016/j.jaad.2007.06.045
Etiology of Acne Vulgaris
The most common trigger is:
Puberty
During puberty, surges in androgens stimulate sebum production and hyperproliferation of keratinocytes.
Other triggers include:
Hormonal changes that occur with pregnancy or the menstrual cycle
Occlusive cosmetics, cleansers, lotions, and clothing
High humidity and sweating
Associations between acne exacerbations and inadequate face washing, masturbation, eating chocolate, and sexual activity are unfounded. Some studies suggest a possible association with consumption of dairy (1) or high-glycemic load diets (2). Acne may abate in summer months because of sunlight’s anti-inflammatory effects. Proposed associations between acne and hyperinsulinism (3, 4) require further investigation. Some medications (eg, glucocorticoids, lithium, phenytoin, isoniazid) worsen acne or cause acneiform eruptions.
Etiology references
1. Adebamowo CA, Spiegelman D, Berkey CS, et al. Milk consumption and acne in teenaged boys. J Am Acad Dermatol. 2008;58(5):787-793. doi: 10.1016/j.jaad.2007.08.049
2. Smith RN, Mann NJ, Braue A, et al. The effect of a high-protein, low glycemic-load diet versus a conventional, high glycemic-load diet on biochemical parameters associated with acne vulgaris: A randomized, investigator-masked, controlled trial. J Am Acad Dermatol. 2007;57(2):247-256. doi: 10.1016/j.jaad.2007.01.046
3. Vora S, Ovhal A, Jerajani H, et al. Correlation of facial sebum to serum insulin-like growth factor-1 in patients with acne. Br J Dermatol. 2008;159(4):990-991. doi: 10.1111/j.1365-2133.2008.08764.x
4. Nagpal M, De D, Handa S, et al. Insulin resistance and metabolic syndrome in young men with acne. JAMA Dermatol. 2016;152(4):399-404. doi: 10.1001/jamadermatol.2015.4499
Pathophysiology of Acne Vulgaris
Acne occurs through the interplay of 4 major factors:
Excess sebum production
Follicular plugging with sebum and keratinocytes
Colonization of follicles by Cutibacterium acnes (formerly Propionibacterium acnes), a normal human anaerobe
Release of multiple inflammatory mediators
Both genetic and environmentally mediated inflammatory factors can contribute to the development of acne (1). Twin studies suggest that acne is heritable, with high concordance in sebum excretion and acne severity among monozygotic twins (2). A positive family history of severe acne is also a significant risk factor (3). Cutaneous microbiome dysbiosis upregulates innate immune responses via the expression and activation of protease-activated receptors, tumour necrosis factor (TNF)-receptors, and toll-like receptors, along with the production of specific substances (eg, interferons, TNF, interleukins [eg, IL-8, IL-12, IL-1], and matrix metalloproteinases [MMPs] by keratinocytes) (4). Th17-mediated pathways may also be upregulated (5). These factors cause chronic local inflammatory changes, dysbiosis, dysseborrhea, and hyperkeratinization of the pilosebaceous unit; acting together, these changes lead to the formation of comedones. See Etiology of Acne Vulgaris for environmental triggers of inflammation.
Acne can be classified as:
Noninflammatory: Characterized by comedones
Inflammatory: Characterized by papules, pustules, nodules, and cysts
Noninflammatory acne
Comedones are dilated hair follicles filled with sebum, desquamated keratinocytes, and bacteria. Although comedones appear noninflammatory themselves, they are the precursor lesions for the development of inflammatory acne. Comedones are termed open or closed depending on whether the follicle is dilated or closed at the skin surface. Sebaceous plugs are easily extruded from open comedones but are more difficult to remove from closed comedones.
Inflammatory acne
Papules and pustules occur when C. acnes colonizes the comedones, breaking down sebum into free fatty acids that irritate the follicular epithelium and eliciting an inflammatory response by neutrophils and then lymphocytes, which further disrupts the epithelium. The inflamed follicle ruptures into the dermis (sometimes precipitated by physical manipulation or harsh scrubbing), where the comedo contents elicit a further local inflammatory reaction, producing papules. If the inflammation is intense, grossly purulent pustules occur.


This illustration of a section through human skin shows a blackhead (open comedo) in acne. At the upper center is a keratin plug (black), and beneath it is trapped sebum (yellow), forming a raised pustule. A hair follicle (lower left) and an actively secreting sebaceous gland (lower right) are shown.
JOHN BAVOSI/SCIENCE PHOTO LIBRARY
Nodules and cysts are other manifestations of inflammatory acne. Nodules are deeper lesions that may involve > 1 contiguous follicle, and cysts are large fluctuant nodules containing fluid (typically pus).
Pathophysiology references
1. Zaenglein AL. Acne Vulgaris. N Engl J Med. 2018;379(14):1343-1352. doi:10.1056/NEJMcp1702493
2. Bataille V, Snieder H, MacGregor AJ, et al. The influence of genetics and environmental factors in the pathogenesis of acne: a twin study of acne in women. J Invest Dermatol. 2002;119(6):1317-1322. doi:10.1046/j.1523-1747.2002.19621.x
3. Di Landro A, Cazzaniga S, Parazzini F, et al. Family history, body mass index, selected dietary factors, menstrual history, and risk of moderate to severe acne in adolescents and young adults. J Am Acad Dermatol. 2012;67(6):1129-1135. doi:10.1016/j.jaad.2012.02.018
4. Dréno B. What is new in the pathophysiology of acne, an overview. J Eur Acad Dermatol Venereol. 2017;31 Suppl 5:8-12. doi:10.1111/jdv.14374
5. Mias C, Mengeaud V, Bessou-Touya S, et al. Recent advances in understanding inflammatory acne: Deciphering the relationship between Cutibacterium acnes and Th17 inflammatory pathway. J Eur Acad Dermatol Venereol. 2023;37 Suppl 2:3-11. doi:10.1111/jdv.18794
Symptoms and Signs of Acne Vulgaris
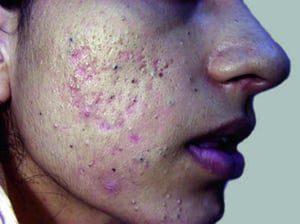
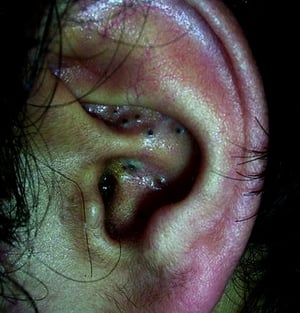
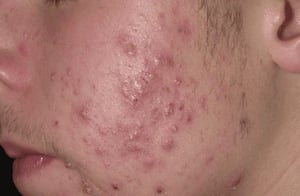
The clinical features of acne include a spectrum of primary lesion types, beginning with comedones and potentially progressing to papules, pustules, nodules, and/or cyst-like lesions. Secondary changes may also occur, including erythema, scarring, and postinflammatory hyperpigmentation. Lesion types can frequently coexist at different stages.
Skin lesions and scarring can be a source of significant emotional distress. Nodules and cysts can be painful.
Comedones appear as whiteheads or blackheads. Whiteheads (closed comedones) are flesh-colored or whitish palpable lesions 1 to 3 mm in diameter; blackheads (open comedones) are similar in appearance but with a dark center.

© Springer Science+Business Media

© Springer Science+Business Media

Pustules are elevated, usually yellow-topped lesions that contain pus. Scattered pustules appear on the face of this person with acne.
Pustules are elevated, usually yellow-topped lesions that contain pus. Scattered pustules appear on the face of this pe
Photo provided by Thomas Habif, MD.

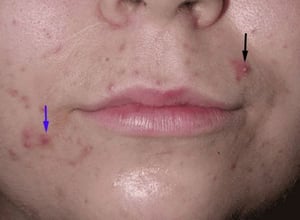
Acne most commonly manifests as comedones (whiteheads or blackheads) and also as papules (blue arrow) and pustules (black arrow).
Acne most commonly manifests as comedones (whiteheads or blackheads) and also as papules (blue arrow) and pustules (bla
Photo provided by Thomas Habif, MD.

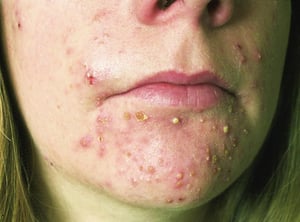
Papules and crusts are also visible.
Papules and crusts are also visible.
© Springer Science+Business Media

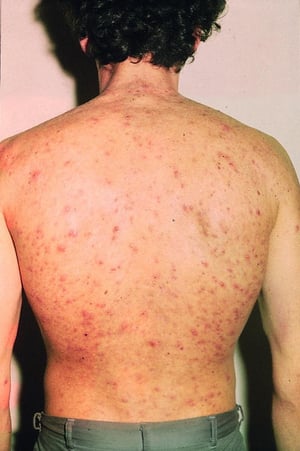
Papules and comedones are present.
Papules and comedones are present.
© Springer Science+Business Media

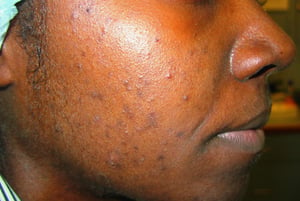
Erythematous pustules and papules along with postinflammatory hyperpigmentation and scarring are present on the face.
Erythematous pustules and papules along with postinflammatory hyperpigmentation and scarring are present on the face.
© Springer Science+Business Media
© Springer Science+Business Media
© Springer Science+Business Media
Pustules are elevated, usually yellow-topped lesions that contain pus. Scattered pustules appear on the face of this person with acne.
Pustules are elevated, usually yellow-topped lesions that contain pus. Scattered pustules appear on the face of this pe
Photo provided by Thomas Habif, MD.
Acne most commonly manifests as comedones (whiteheads or blackheads) and also as papules (blue arrow) and pustules (black arrow).
Acne most commonly manifests as comedones (whiteheads or blackheads) and also as papules (blue arrow) and pustules (bla
Photo provided by Thomas Habif, MD.
Papules and crusts are also visible.
Papules and crusts are also visible.
© Springer Science+Business Media
Papules and comedones are present.
Papules and comedones are present.
© Springer Science+Business Media
Erythematous pustules and papules along with postinflammatory hyperpigmentation and scarring are present on the face.
Erythematous pustules and papules along with postinflammatory hyperpigmentation and scarring are present on the face.
© Springer Science+Business Media
Papules and pustules are erythematous lesions 2 to 5 mm in diameter. Papules are relatively deep. Pustules are more superficial.
Nodules are larger, deeper, and more solid than papules. Such lesions may resemble inflamed epidermoid cysts, although they lack true cystic structure.
Cysts are fluid-filled (typically suppurative) nodules. Rarely, cysts form deep abscesses. Long-term cystic acne can cause scarring that manifests as tiny and deep pits (icepick scars), larger pits, shallow depressions, or hypertrophic scarring or keloids.
Postinflammatory hyperpigmentation may occur after inflammatory acne lesions resolve.

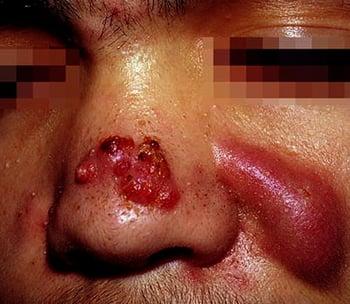

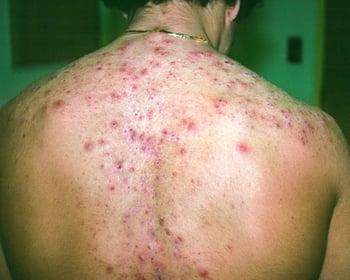
This photo shows suppurative nodules consistent with cystic acne.
Acne conglobata is the most severe form of acne vulgaris, affecting men more than women. Patients have abscesses, draining sinuses, fistulated comedones, and keloidal and atrophic scars. The back and chest are severely involved. The arms, abdomen, buttocks, and even the scalp may be affected.

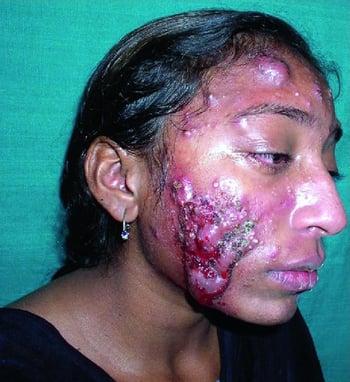
This photo shows acne conglobata, the most severe form of acne vulgaris, on the face. Abscesses and keloidal scars are visible.
Acne fulminans is acute, febrile, ulcerative acne, characterized by the sudden appearance of confluent abscesses leading to hemorrhagic necrosis. Leukocytosis, arthralgias, and arthritis may also be present.

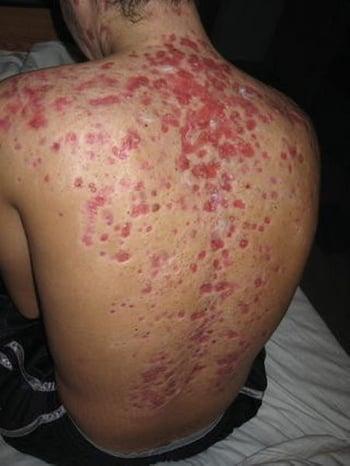
This photo shows confluent and nonconfluent ulcerations resulting from acne fulminans.
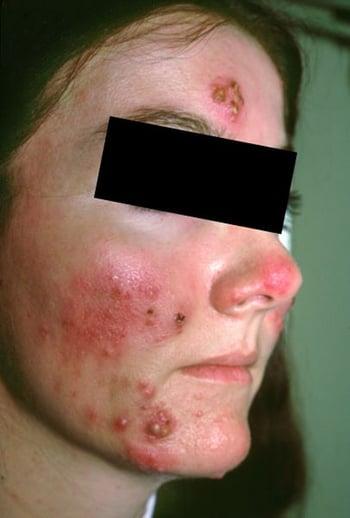
Pyoderma faciale (also called rosacea fulminans) occurs suddenly on the midface of young women. It may be analogous to acne fulminans. The eruption consists of erythematous plaques and pustules, involving the chin, cheeks, and forehead. Papules and nodules may develop and become confluent.

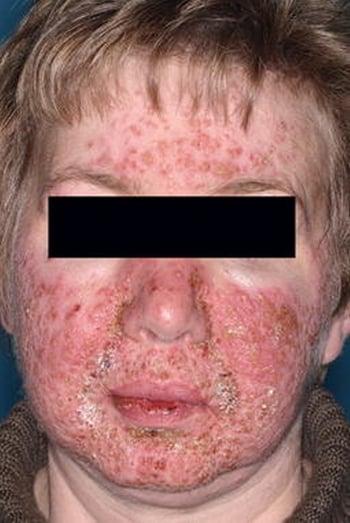
This photo shows pyoderma faciale with erythematous plaques, papules, pustules, and confluent nodules.

Diagnosis of Acne Vulgaris
History and physical examination
Assessment for contributing factors (eg, hormonal, mechanical, or medication-related)
Determination of severity (mild, moderate, severe)
Assessment of psychosocial impact
The diagnosis of acne vulgaris is primarily based on the history and physical examination. The history should include questions about medication exposures (eg, drug-induced acne) or family history, symptoms, and signs of hyperandrogenism or other disease associated with acne (eg, SAPHO [synovitis, acne, pustulosis, hyperostosis, and osteitis] syndrome).
Differential diagnoses include rosacea (in which no comedones are seen), glucocorticoid-induced acne (which lacks comedones and in which pustules are usually in the same stage of development), perioral dermatitis (usually with a more perioral and periorbital distribution), and acneiform drug eruptions (see table ).
In general, clinicians classify severity (eg, mild, moderate, severe) based on the number and types of lesions and their overall clinical impression. However, there are many clinical grading systems that can be used for the grading of the severity of acne (1, 2). One of the most commonly used systems is the Investigator Global Assessment (IGA). However, most clinicians can easily define acne grading by using their own judgment of mild, moderate, or severe in practice. Their grading should include location (eg, face, back, chest, neck); some include whether or not there is presence of scarring. For an example of a clinical grading approach, see Classification of Acne Severity.
Routine endocrinologic testing is usually not necessary for most patients (1). However, testing may be indicated for patients in whom there is concern for other hormonal abnormalities because of finding such as hirsutism or irregular menses. Laboratory evaluation for polyendocrine metabolic ovarian syndrome (PMOS), which is the most common hormonal abnormality in young females, or other hormonal conditions such as congenital adrenal hyperplasia can be performed with testing generally on day 3 of menses. Testing should include free and total testosterone, 17-hydroxyprogesterone, androstenedione, sex hormone binding globulin, prolactin, and dehydroepiandrosterone (DHEA).
Classification of Acne Severity
Severity | Definition |
|---|---|
Mild | < 20 comedones, or < 15 inflammatory lesions, or < 30 total lesions |
Moderate | 20 to 100 comedones, or 15 to 50 inflammatory lesions, or 30 to 125 total lesions |
Severe | > 5 cysts, or total comedone count > 100, or total inflammatory lesion count > 50, or > 125 total lesions |
Diagnosis references
1. Reynolds RV, Yeung H, Cheng CE, et al. Guidelines of care for the management of acne vulgaris. J Am Acad Dermatol. 2024;90(5):1006.e1-1006.e30. doi:10.1016/j.jaad.2023.12.017
2. Bae IH, Kwak JH, Na CH, et al. A Comprehensive Review of the Acne Grading Scale in 2023. Ann Dermatol. 2024;36(2):65-73. doi: 10.5021/ad.23.094
Treatment of Acne Vulgaris
Comedones: Topical tretinoin
Mild inflammatory acne: Topical retinoid, topical antibiotic, benzoyl peroxide (BPO)
Moderate acne: Oral antibiotic plus topical therapy as for mild acne
Severe acne: Oral isotretinoin
Cystic acne: Intralesional triamcinolone
For all types: adjunctive measures (peels, hormone therapies, light therapy, dietary modifications)
Treatment approaches in acne are guided by clinical severity (eg, extent, scarring) and should also address contributing factors (eg, medication-related acne) and psychological distress (1).
A variety of topical and systemic agents directed at reducing sebum production, comedone formation, inflammation, and bacterial counts and at normalizing keratinization are used (see figure and table ). Acne treatment usually follows a step-wise approach based on severity, escalating from topical therapy for mild disease, to systemic agents for moderate disease, to isotretinoin for severe or treatment-resistant disease. In addition, a multimodal approach combining agents with different mechanisms of action is usually recommended to optimize efficacy and reduce antibiotic resistance (1). Monotherapy, particularly with topical antibiotics, is not recommended.
Affected areas should be cleansed once or twice a day, but additional washing, use of antibacterial soaps, and scrubbing confer no added benefit and may be harmful.
Acne management can be supported by the use of adjunctive measures such as chemical peels, hormone therapies, medical devices, and dietary modifications. Chemical peeling agents such as sulfur, salicylic acid, glycolic acid, and resorcinol can be useful. Combined (estrogen plus a progestin) oral contraceptives are effective in treating inflammatory and noninflammatory acne (2), and spironolactone is another antiandrogen that is often useful in women (3, 4). Various light therapies, with and without topical photosensitizers, have been used effectively, mostly for inflammatory acne, but supporting evidence is not high quality (5). A lower-glycemic diet and moderation of dairy intake might be considered for treatment-resistant adolescent acne, but the effectiveness of these measures in treating acne remains controversial (6).
Treatment should involve educating the patient and tailoring the plan to one that is realistic for the patient. Treatment failure can frequently be attributed to lack of adherence to the plan and also to lack of follow-up. Consultation with a dermatologist may be necessary.
How Various Medications Work in Treating Acne


Medications Used to Treat Acne
Medication | Adverse Effects | Comments |
|---|---|---|
Topical antibacterials | ||
Benzoyl peroxide 2.5%, 5%, and 10% gel, lotion, or wash | Dry skin Possible bleaching of clothing and hair Allergic reactions (rarely) | Comedolytic and antibacterial with very low to no development of resistance Should be used in all patients if tolerated Gel product usually preferred |
Benzoyl peroxide/clindamycin gel | Dry skin Possible bleaching of clothing and hair Allergic reactions (rarely) | Combination products can be used |
Benzoyl peroxide/erythromycin gel | Dry skin Possible bleaching of clothing and hair Allergic reactions (rarely) | Some forms must be kept refrigerated |
Clindamycin 1% gel, solution, or lotion | Diarrhea (rarely) | Should be avoided in patients with inflammatory bowel disease |
Dapsone 5% and 7.5% gel | Temporary skin yellowing when used in conjunction with benzoyl peroxide | Very rarely causes methemoglobinemia Limit use to over 12 years of age Limit use to face only |
Erythromycin 1.5 to 2% (multiple vehicles) | Local irritation (rarely) | Well-tolerated, but frequent development of bacterial resistance |
Minocycline foam 4% | Irritation, dry skin, erythema | Foam propellant is flammable. Avoid fire/flame and smoking immediately after application. |
Topical comedolytics and exfoliants | ||
Adapalene 0.1% gel, cream, lotion; 0.3% gel* | Some erythema, burning, and increased sun sensitivity | As effective as tretinoin but less irritating Requires use of protective clothing and sunscreen |
Azelaic acid 20% cream | Possible lightening of skin | Minimally irritating May be used by itself or with tretinoin Should be used cautiously in patients with dark skin because of skin-lightening effects |
Glycolic acid 5–10% | Stinging Mild irritation | Over-the-counter product in cream, lotion, or solution; adjunct therapy but no longer commonly used |
Tazarotene 0.05% or 0.1% cream or gel* | Skin irritation Increased sun sensitivity | When tazarotene is started, apparent worsening of acne, with improvement possibly taking 3 to 4 weeks to occur Requires use of protective clothing and sunscreen Should be avoided during pregnancy |
Tretinoin 0.025%, 0.05%, and 0.1% cream; 0.05% liquid; 0.01%, 0.025%, and 0.1% gel* | Skin irritation (with dryness, erythema, and scaling) Increased sun sensitivity | Initiate treatment at a low strength (eg, 0.025% cream) and increase if ineffective; if irritation occurs, strength, frequency, or both should be reduced When tretinoin is started, apparent worsening of acne, with improvement possibly taking 3 to 4 weeks to occur Requires use of protective clothing and sunscreen Should be avoided during pregnancy |
Trifarotene 0.005% cream* | Dryness, erythema, and scaling of the skin Increased sun sensitivity | Requires use of protective clothing and sunscreen |
Oral antibiotics | ||
Azithromycin | Stomach upset | Frequent development of bacterial resistance |
Cefadroxil | Stomach upset | Second-line agent for patients who have failed tetracyclines; useful in pregnant patients with inflammatory acne |
Cephalexin | Stomach upset | Second-line agent for patients who have failed tetracyclines; useful in pregnant patients with inflammatory acne |
Doxycycline | Increased sun sensitivity | Good first-line medication in terms of efficacy Requires use of protective clothing and sunscreen |
Erythromycin | Stomach upset | Frequent development of bacterial resistance |
Minocycline | Headache Dizziness Skin discoloration | Most commonly prescribed antibiotic in many settings |
Sarecycline | Similar to other tetracycline medications | Narrow spectrum of activity targeting acne-specific bacteria |
Tetracycline | Increased sun sensitivity | Inexpensive and safe, but must be taken on an empty stomach Requires use of protective clothing and sunscreen |
Trimethoprim/sulfamethoxazole (TMP-SMX), also called cotrimoxazole | Adverse drug reactions (eg, stomach upset, skin rashes) | Development of bacterial resistance |
Oral retinoid | ||
Isotretinoin | Possible harm to a developing fetus (contraindicated during pregnancy) Possible effect on blood cells, the liver, and fat (triglyceride and cholesterol) levels Dry eyes, chapped lips, drying of mucous membranes Pain or stiffness of large joints and lower back with high dosages Associated with rare mood reactions in adolescents with a pre-existing psychiatric disorder | For sexually active women, requires a pregnancy test before the start of therapy with isotretinoin and at monthly intervals during use of the medication plus use of 2 forms of contraception or sexual abstinence, beginning 1 month before the medication is started, continued during medication use, and for 1 month after stopping the medication Requires periodic complete blood count, liver tests, fasting glucose, and lipid profile |
Antiandrogens | ||
Clascoterone 1% cream | Erythema, scaling or dryness, and pruritus | For treatment of acne in patients 12 years of age and older |
Combined (estrogen plus a progestin) oral contraceptives | Hypertension, thromboembolic events Weight gain Nausea Breakthrough bleeding Headache | For treatment of acne in females |
Spironolactone | Light-headedness Increased urination Breast tenderness Nausea | For treatment of acne in females |
*Topical retinoids (vitamin A derivatives) †Bienenfeld A, Nagler AR, Orlow SJ: Oral antibacterial therapy for acne vulgaris: An evidence-based review. Am J Clin Dermatol 18(4):469–490, 2017. doi: 10.1007/s40257-017-0267-z | ||
Mild acne
Treatment of mild acne should be continued for 6 to 12 weeks or until lesions respond. Maintenance treatment is usually necessary to maintain control.
Single-agent therapy with topical retinoids (eg, tretinoin) may be sufficient for the treatment of mild acne that is exclusively comedonal. Daily adapalene gel, tazarotene cream or gel, azelaic acid cream, and glycolic or salicylic acid are alternatives for patients who cannot tolerate topical tretinoin. Adverse effects include erythema, burning, stinging, and peeling. Adapalene, trifarotene, and tazarotene are retinoids; like tretinoin, they are usually somewhat irritating and photosensitizing. Azelaic acid has comedolytic and antibacterial properties via an unrelated mechanism and may be synergistic with retinoids.
Combination therapy (eg, a combination of tretinoin with benzoyl peroxide, a topical antibiotic, or both) should be used to treat mild papulopustular (inflammatory) acne. Typical topical antibiotics used include erythromycin and clindamycin. Combining benzoyl peroxide with these antibiotics can help limit development of resistance. Glycolic acid may be used instead of or in addition to tretinoin but is no longer used commonly. Treatments have no significant adverse effects other than drying and irritation (and rare allergic reactions to benzoyl peroxide). A combination of clindamycin phosphate, adapalene, and benzoyl peroxide is available in the United States.
Physical extraction of comedones using a comedone extractor is an option for patients unresponsive to topical treatment. Comedone extraction may be performed by a physician, nurse, or physician assistant. One end of the comedone extractor is like a blade or bayonet that punctures the closed comedone. The other end exerts pressure to extract the comedone.
Oral antibiotics (eg, tetracyclines) are generally reserved for moderate and severe acne, but may be used when wide distribution of lesions makes topical therapy impractical, or if there is clinical concern for worsening or progression.
Clascoterone is a topical androgen receptor inhibitor for the treatment of acne. It can be used in patients 12 years of age and older. Clascoterone 1% cream is applied 2 times a day. Adverse effects include erythema, scaling or dryness, and pruritus; although hyperkalemia and hypothalamic-pituitary-adrenal axis suppression have been predicted based on its mechanism, these effects have not been noticed clinically (7).
Moderate acne
Oral systemic therapy with antibiotics is typically included in the treatment of moderate acne (1). Antibiotics effective for acne include tetracyclines (eg, tetracycline, minocycline, doxycycline, sarecycline), and macrolides (eg, erythromycin, azithromycin). Full benefit takes ≥ 12 weeks. Systemic antibiotic use should be limited when possible, to reduce the risks of resistance and other antibiotic-related complications.
Topical therapy, as for mild acne, is usually used concomitantly with oral antibiotics. Topical agents may less commonly be used independently, such as when oral agents are discontinued but treatment must be continued.
Doxycycline and minocycline are preferred antibiotic medications; both can be taken with food. Tetracycline is also reasonable, but it cannot be taken with food and may have lower efficacy than doxycycline and minocycline. The dosage of doxycycline and minocycline is 50 to 100 mg orally 2 times a day. Doxycycline may cause photosensitivity, and minocycline may have more adverse effects with chronic use, including drug-induced lupus and hyperpigmentation. To reduce the development of antibiotic resistance after control is achieved (usually 2 to 3 months), the dose is tapered as much as possible to maintain control. Sarecycline is a newer tetracycline antibiotic (dosing is weight-based at 1.5 mg/kg; typical doses range from 60 mg to 150 mg orally once a day) (1). Antibiotics may be discontinued if topical therapy maintains control.
Macrolides (erythromycin and azithromycin) are alternative antibiotics, but they are more likely to cause gastrointestinal adverse effects and antibiotic resistance. Some clinicians also use trimethoprim/sulfamethoxazole (TMP-SMX), also called cotrimoxazole. However, antibacterial resistance may develop, and TMP-SMX can cause rare adverse drug reactions.
Long-term use of antibiotics may cause a gram-negative pustular folliculitis around the nose and in the center of the face. This uncommon superinfection may be difficult to clear and is best treated with oral isotretinoin after discontinuing the oral antibiotic. Ampicillin is an alternative treatment for gram-negative folliculitis. In women, prolonged antibiotic use can cause candidal vaginitis; if local and systemic therapy does not eradicate this problem, antibiotic therapy for acne must be stopped.
In a female patient who is unresponsive to oral antibiotics, a trial of oral antiandrogens (combined oral contraceptives and/or spironolactone) may be considered.
Severe acne
Oral isotretinoin is typically reserved for the treatment of patients with moderate acne in whom other oral and topical therapies have been unsuccessful and for those with severe inflammatory acne (1). Dosage of isotretinoin is usually 1 mg/kg in total once a day for 16 to 20 weeks; the total dose may also be administered divided equally twice a day. If adverse effects make this dosage intolerable (see ), it may be reduced to 0.5 mg/kg once a day. After therapy, acne may continue to improve.
Many patients do not require a second course of treatment; when needed, it is resumed only after the medication has been stopped for 2 or more months, except in severe cases when it may be resumed earlier. Retreatment is required more often if the initial dosage is low (0.5 mg/kg). With this dosage (which is very popular in Europe), fewer adverse effects occur, but prolonged therapy is usually required. Cumulative dosing has gained support; a total dosage of 120 to 150 mg/kg resulted in lower recurrence rates, and some experts suggest a higher cumulative dose of 220 mg/kg (8).
Isotretinoin is remarkably effective in practice; however, the quality of evidence to support its use is low (1, 9). Its use is also limited by adverse effects, including dryness of conjunctivae and mucosae of the genitals, chapped lips, arthralgias, depression, elevated lipid levels, and the risk of birth defects if treatment occurs during pregnancy. Hydration with water followed by petrolatum application usually alleviates mucosal and cutaneous dryness. Arthralgias (mostly of large joints or the lower back) often occur. Increased risk of depression and suicide has been much publicized but has not been supported by population-level evidence, and treatment may actually improve psychiatric outcomes (10). However, rare mood reactions can occur, particularly in adolescents and those with a pre-existing history of psychiatric disorders, and close monitoring is warranted. Although the risk of new or worsened inflammatory bowel disease (Crohn disease and ulcerative colitis) has been proposed to be associated with use of isotretinoin, such an association now appears unlikely (11).
Baseline complete blood count, liver tests, triglyceride, and cholesterol levels should be obtained before treatment. Each should be reassessed at 4 to 8 weeks and, unless abnormalities are noted, need not be repeated until the end of treatment. Triglycerides rarely increase to a level at which the medication should be stopped. Liver function is seldom affected. Because isotretinoin is teratogenic, women of childbearing age must be told that they are required to use 2 methods of contraception for 1 month before treatment, during treatment, and for at least 1 month after stopping treatment. Tests excluding pregnancy should be performed before beginning therapy and monthly until 1 month after therapy stops.
Cystic acne
Intralesional glucocorticoid injections (eg, 0.1 mL triamcinolone acetonide suspension 2.5 mg/mL [the 10 mg/mL suspension must be diluted]) is indicated for patients with firm (cystic) acne who seek quick clinical improvement with reduced scarring. Local atrophy may occur but is usually transient. For isolated, very boggy lesions, incision and drainage are often beneficial but may result in residual scarring.
Other forms of acne
Pyoderma faciale is treated with oral glucocorticoids and isotretinoin.
Acne fulminans is commonly treated with oral glucocorticoids and systemic antibiotics.
Acne conglobata is treated with oral isotretinoin and systemic glucocorticoids if severe and if systemic antibiotics fail.
For acne caused by endocrine abnormalities (eg, polycystic ovary syndrome, virilizing adrenal tumors in females), antiandrogens are indicated. Spironolactone, which has some antiandrogen effects, is sometimes prescribed to treat acne. Cyproterone acetate is used in Europe. When other measures fail, an estrogen/progestin–containing contraceptive may be tried; therapy ≥ 6 months is needed to evaluate effect.
Scarring
Small scars can be treated with chemical peels, laser resurfacing, microneedling, or dermabrasion. Deeper, discrete scars can be excised. Wide, shallow depressions can be treated with subcision or injection of collagen or another filler. Fillers, including collagen, hyaluronic acid, and polymethylmethacrylate, are temporary and must be repeated periodically.
Treatment references
1. Reynolds RV, Yeung H, Cheng CE, et al. Guidelines of care for the management of acne vulgaris. J Am Acad Dermatol. 2024;90(5):1006.e1-1006.e30. doi:10.1016/j.jaad.2023.12.017
2. Koltun W, Maloney JM, Marr J, et al. Treatment of moderate acne vulgaris using a combined oral contraceptive containing ethinylestradiol 20 μg plus drospirenone 3 mg administered in a 24/4 regimen: a pooled analysis. Eur J Obstet Gynecol Reprod Biol. 2011 Apr;155(2):171-5. doi: 10.1016/j.ejogrb.2010.12.027. Epub 2011 Feb 2.
3. Grandhi R, Alikhan A. Spironolactone for the Treatment of Acne: A 4-Year Retrospective Study. Dermatology. 2017;233(2-3):141-144, 2017. doi: 10.1159/000471799
4. Roberts EE, Nowsheen S, Davis MDP, et al. Treatment of acne with spironolactone: A retrospective review of 395 adult patients at Mayo Clinic, 2007-2017. J Eur Acad Dermatol Venereol. 2020;34(9):2106-2110. doi: 10.1111/jdv.16302
5. Barbaric J, Abbott R, Posadzki P, et al. Light therapies for acne. Cochrane Database Syst Rev. 2016;9(9):CD007917. doi: 10.1002/14651858.CD007917.pub2
6. Dall'Oglio F, Nasca M, Fiorentini F, Micali G. Diet and acne: Review of the evidence from 2009 to 2020. Int J Dermatol. 2021;60(6):672–685. doi: 10.1111/ijd.15390
7. Hebert A, Thiboutot D, Stein Gold L, et al. Efficacy and safety of topical clascoterone cream, 1%, for treatment in patients with facial acne: Two phase 3 randomized clinical trials. JAMA Dermatol. 2020;156(6):621–630. doi:10.1001/jamadermatol.2020.0465
8. Blasiak RC, Stamey CR, Burkhart CN, et al. High-dose isotretinoin treatment and the rate of retrial, relapse, and adverse effects in patients with acne vulgaris. JAMA Dermatol. 2013;149(12):1392–1398. doi: 10.1001/jamadermatol.2013.6746
9. Costa CS, Bagatin E, Martimbianco ALC, et al. Oral isotretinoin for acne. Cochrane Database Syst Rev. 2018;11(11):CD009435. Published 2018 Nov 24. doi:10.1002/14651858.CD009435.pub2
10. Tan NKW, Tang A, MacAlevey NCYL, et al. Risk of Suicide and Psychiatric Disorders Among Isotretinoin Users: A Meta-Analysis. JAMA Dermatol. 2024;160(1):54-62. doi:10.1001/jamadermatol.2023.4579
11. Lee SY, Jamal MM, Nguyen ET, et al. Does exposure to isotretinoin increase the risk for the development of inflammatory bowel disease? A meta-analysis. Eur J Gastroenterol Hepatol. 2016;28(2):210–216. doi: 10.1097/MEG.0000000000000496
Prognosis for Acne Vulgaris
Acne of any severity usually resolves spontaneously by a person's early to mid 20s, but a substantial minority of patients, usually women, may have acne into their 40s (1); options for treatment may be limited because of childbearing. Many adults can occasionally develop mild, isolated acne lesions. Noninflammatory and mild inflammatory acne usually heals without scars. Moderate to severe inflammatory acne heals but often leaves scarring. Scarring is not only physical; acne may be a huge emotional stressor for adolescents who may withdraw, using the acne as an excuse to avoid difficult personal adjustments. Supportive counseling for patients and parents may be indicated in severe cases.
Prognosis reference
1. Collier CN, Harper JC, Cafardi JA, et al: The prevalence of acne in adults 20 years and older. J Am Acad Dermatol 58(1):56-59, 2008. doi: 10.1016/j.jaad.2007.06.045
Key Points
If noninflammatory, acne is characterized by comedones and, if inflammatory, by papules, pustules, nodules, and cysts.
Mild and moderate acne usually heals without scarring by the mid 20s.
Patients should avoid triggers (eg, occlusive cosmetics and clothing, cleansers, lotions, high humidity, some medications, chemicals, possibly a high intake of dairy products or a high-glycemic diet).
Consider the psychological as well as the physical effects of acne.
Prescribe a topical comedolytic (eg, tretinoin) plus, for inflammatory acne, benzoyl peroxide, a topical antibiotic, or both.
Prescribe an oral antibiotic for moderate acne and oral isotretinoin for severe acne.
Treat cystic acne with intralesional triamcinolone as needed for acute lesions.
Drug Information for the Topic




