


Restrictive cardiomyopathy encompasses a heterogeneous group of diseases characterized by restrictive physiology, a disproportionate rise in ventricular pressures in response to small increases in ventricular filling volume. One (most commonly the left) or both ventricles may be affected. Symptoms include fatigue, exertional dyspnea, abdominal distension, and lower extremity edema. The diagnosis is established by echocardiography, cardiac MRI, and, in select cases, by cardiac catheterization. Treatment is directed at the underlying cause and symptom relief (eg, diuretics for congestion).
A cardiomyopathy is a primary disorder of the heart muscle (see also Overview of Cardiomyopathies).
Restrictive cardiomyopathy (RCM) is the least prevalent form of cardiomyopathy (1, 2).
Restrictive cardiomyopathy can affect one or both ventricles with diffuse or segmental distribution.
General references
1. Muchtar E, Blauwet LA, Gertz MA. Restrictive Cardiomyopathy: Genetics, Pathogenesis, Clinical Manifestations, Diagnosis, and Therapy. Circ Res. 2017;121(7):819-837. doi:10.1161/CIRCRESAHA.117.310982
2. Rapezzi C, Aimo A, Barison A, et al. Restrictive cardiomyopathy: definition and diagnosis. Eur Heart J. 2022;43(45):4679-4693. doi:10.1093/eurheartj/ehac543
Etiology of Restrictive Cardiomyopathy
Restrictive cardiomyopathies can be classified into 4 categories according to etiology (1, 2):
Infiltrative (eg, amyloidosis, sarcoidosis)
Non-infiltrative (eg, idiopathic, systemic sclerosis)
Storage diseases (eg, Fabry disease, hemochromatosis)
Endomyocardial disorders (eg, endomyocardial fibrosis, hypereosinophilic syndrome, carcinoid syndrome, metastatic cancer, medications [hydroxychloroquine, ergotamine, methysergide])
Restrictive cardiomyopathy is not always a primary cardiac disorder. Primary forms of RCM include idiopathic restrictive cardiomyopathy and endomyocardial fibrosis, whereas the remaining etiologies are considered secondary. Both inherited and acquired forms are recognized (1).
Although the etiology is frequently idiopathic, RCM may arise as the consequence of systemic or genetic disorders (see table . Histopathology typically involves abnormalities of the endocardium, myocardium, or both, resulting in increased ventricular stiffness and reduced compliance.
Infiltrative conditions such as systemic amyloidosis (including both light-chain amyloidosis with cardiomyopathy [AL-CM] and transthyretin amyloidosis with cardiomyopathy [ATTR-CM]) and iron overload cardiomyopathy involve extracardiac tissues in addition to the myocardium. Infiltrative or storage diseases may affect other cardiac structures, including the conduction system.
Distinct clinicopathologic entities within the spectrum of RCM demonstrate characteristic patterns of involvement. Hypereosinophilic syndrome affecting the heart (formerly known as Löffler endocarditis) is characterized by an initial phase of eosinophilic myocarditis, followed by mural thrombus formation along the injured endocardium, and eventual progression to endomyocardial fibrosis and fibrotic remodeling of valvular structures. Endocardial fibroelastosis, typically observed in infants and young children, predominantly affects the left ventricle and is marked by diffuse endocardial thickening. In contrast, endomyocardial fibrosis, which is more prevalent in equatorial countries, commonly involves both ventricles and represents a major cause of restrictive physiology worldwide (3).
Some Causes of Restrictive Cardiomyopathy
Cause | Examples |
|---|---|
Endomyocardial disorders | Carcinoid heart disease Endocardial fibroelastosis Endomyocardial fibrosis Hypereosinophilic syndrome (Löffler endocarditis) Metastatic cancer Medications (eg, hydroxychloroquine, ergotamine, methysergide, mercurial agents, busulfan) Radiation |
Infiltrative disorders | Amyloidosis (including light-chain amyloidosis and transthyretin amyloidosis) Primary hyperoxaluria |
Non-infiltrative disorders | Idiopathic restrictive cardiomyopathy |
Storage diseases | Gaucher disease Mucopolysaccharidosis type I (Hurler syndrome) and mucopolysaccharidosis type II (Hunter syndrome) Nieman-Pick disease |
Data from Gowda SN, Ali HJ, Hussain I. Overview of Restrictive Cardiomyopathies. Methodist Debakey Cardiovasc J 2022;18(2):4-16. Published 2022 Mar 14. doi:10.14797/mdcvj.1078 and Muchtar E, Blauwet LA, Gertz MA. Restrictive Cardiomyopathy: Genetics, Pathogenesis, Clinical Manifestations, Diagnosis, and Therapy. Circ Res. 2017;121(7):819-837. doi:10.1161/CIRCRESAHA.117.310982 | |
Etiology references
1. Gowda SN, Ali HJ, Hussain I. Overview of Restrictive Cardiomyopathies. Methodist Debakey Cardiovasc J. 2022;18(2):4-16. doi:10.14797/mdcvj.1078
2. Muchtar E, Blauwet LA, Gertz MA. Restrictive Cardiomyopathy: Genetics, Pathogenesis, Clinical Manifestations, Diagnosis, and Therapy. Circ Res. 2017;121(7):819-837. doi:10.1161/CIRCRESAHA.117.310982
3. Pereira NL, Grogan M, Dec GW. Spectrum of Restrictive and Infiltrative Cardiomyopathies: Part 2 of a 2-Part Series. J Am Coll Cardiol. 2018;71(10):1149-1166. doi:10.1016/j.jacc.2018.01.017
Pathophysiology of Restrictive Cardiomyopathy
Endomyocardial thickening or myocardial infiltration may affect one, typically the left, or both ventricles. Involvement of the conduction system, including the sinoatrial (SA) and atrioventricular nodes, may result in sinus node dysfunction and varying degrees of atrioventricular (AV) block.
The principal hemodynamic abnormality is diastolic dysfunction due to a stiff, noncompliant left ventricle, leading to impaired diastolic filling, and elevated filling pressures. This in turn causes pulmonary venous hypertension and may lead or contribute to progressive right ventricular dysfunction. Although systolic function is typically preserved in early stages, it may decline with advancing disease. Stroke volume is often relatively fixed due to impaired ventricular filling, rendering cardiac output dependent on heart rate. Chronic elevation of filling pressures leads to biatrial enlargement, predisposing to atrial arrhythmias and functional atrioventricular valve regurgitation. In certain forms, particularly endomyocardial fibrosis, hypereosinophilic syndromes, and cardiac amyloidosis, intracardiac thrombi may form, with risk of systemic embolization.
Symptoms and Signs of Restrictive Cardiomyopathy
Restrictive cardiomyopathy (RCM) typically presents with fatigue, exercise intolerance, exertional dyspnea, orthopnea, palpitations, abdominal distension and peripheral edema. Both atrial and ventricular arrhythmias, as well as conduction abnormalities, are commonly observed (1). Symptoms and signs closely resemble those of constrictive pericarditis.
Normal Jugular Vein Waves
The a wave is caused by right atrial contraction (systole) and is followed by the x descent, which is caused by atrial relaxation. The c wave, an interruption of the x descent, is caused by the transmitted carotid pulse; it is seldom discerned clinically. The v wave is caused by right atrial filling during ventricular systole (tricuspid valve is closed). The y descent is caused by rapid filling of the right ventricle during ventricular diastole before atrial contraction. |

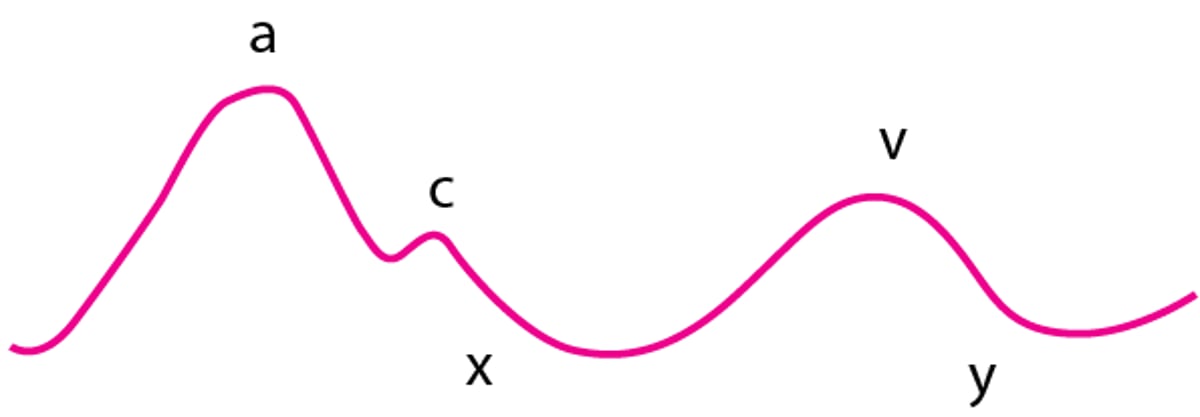
On physical examination, findings include a low-volume and rapid carotid pulse, pulmonary crackles, and pronounced jugular venous distention with a rapid y descent without respiratory variation (absence of a Kussmaul sign) (see figure ). Atrial fibrillation is common (1). Auscultation may reveal a third heart sound (S3) and/or a fourth heart sound (S4), which should be differentiated from the precordial knock associated with constrictive pericarditis. In some patients, a murmur of functional mitral or tricuspid regurgitation is present, reflecting atrial dilation and alterations in chordal structure or ventricular geometry due to myocardial or endocardial infiltration or fibrosis. Pulsus paradoxus is typically absent. In advanced stages, ascites and significant peripheral edema may be evident (2).
Symptoms and signs references
1. Muchtar E, Blauwet LA, Gertz MA. Restrictive Cardiomyopathy: Genetics, Pathogenesis, Clinical Manifestations, Diagnosis, and Therapy. Circ Res. 2017;121(7):819-837. doi:10.1161/CIRCRESAHA.117.310982
2. Pereira NL, Grogan M, Dec GW. Spectrum of Restrictive and Infiltrative Cardiomyopathies: Part 1 of a 2-Part Series. J Am Coll Cardiol. 2018;71(10):1130-1148. doi:10.1016/j.jacc.2018.01.016
Diagnosis of Restrictive Cardiomyopathy
ECG, chest radiograph, and echocardiography
Cardiac MRI
Sometimes left and right heart catheterization with endomyocardial biopsy
Laboratory tests and biopsy of other organ systems as needed
Genetic testing
The diagnosis of restrictive cardiomyopathy (RCM) requires integration of clinical evaluation with multimodality imaging, hemodynamic assessment, laboratory testing, and, in selected cases, tissue characterization. Initial evaluation typically includes electrocardiography, chest radiography, and transthoracic echocardiography, followed by advanced imaging with cardiac MRI. Invasive assessment with right and left heart catheterization and endomyocardial biopsy is reserved for cases in which noninvasive testing is inconclusive or when a specific diagnosis is required to guide therapy.
RCM should be suspected in patients with heart failure and preserved ejection fraction, particularly in the presence of a known systemic disorder associated with myocardial infiltration or fibrosis. However, the underlying disorder may not be obvious on presentation.
Electrocardiographic findings are generally nonspecific and may include evidence of biatrial enlargement (eg, prominent P waves), ST-segment and T-wave abnormalities, and conduction disturbances, the latter raising suspicion for infiltrative disease (1). Depending on etiology, LV voltage can be elevated or low.
On chest radiograph, the heart size is often normal or small but can be enlarged in advanced disease, particularly in conditions such as sarcoid cardiomyopathy or hemochromatosis.
Echocardiography typically shows a non-dilated left ventricle with preserved left ventricular ejection fraction although LV systolic dysfunction may develop in later stages. Biatrial dilation is common, and ventricular wall thickness may be normal or increased, especially with infiltrative processes (1, 2). Tissue Doppler imaging demonstrates impaired diastolic function and elevated LV filling pressures (eg, E/A ratio > 1.5, decreased mitral deceleration time [DT] and mitral annular velocities [e'], elevated E/e'). Additional findings may include thickened valves, pericardial effusion, a plethoric inferior vena cava and inspiratory diastolic flow reversal in the hepatic veins, reflecting impaired right ventricular compliance.
Cardiac MRI provides superior tissue characterization and is particularly useful in differentiating RCM from constrictive pericarditis. Patterns of late gadolinium enhancement can suggest specific etiologies, including infiltrative cardiomyopathies. Parametric mapping techniques (native T1, T2, and T2*) enable quantitative assessment of myocardial composition, facilitating detection of myocardial edema, inflammation, fibrosis, and iron deposition, and may point toward specific diagnoses such as Fabry disease, amyloid cardiomyopathy or iron overload (1, 2).
Complementary imaging modalities may be employed to evaluate for specific causes: fluorodeoxyglucose positron emission tomography is useful for identifying inflammatory processes such as cardiac sarcoidosis, while technetium-99m pyrophosphate scintigraphy supports the diagnosis of transthyretin amyloid cardiomyopathy (2, 3). Light-chain amyloid cardiomyopathy (AL-CM) should be diagnosed (or excluded) using serum and urine protein electrophoresis with immunofixation and serum free light chain analysis as well as tissue biopsy, as nuclear imaging findings may overlap with ATTR-CM. Endomyocardial biopsy may be considered in patients with high clinical suspicion despite negative or equivocal 99mTc-pyrophosphate (Tc-99m PYP) scan, or in patients with a positive Tc-99m PYP scan and an underlying plasma cell dyscrasia (to evaluate for AL amyloid or concomitant AL and ATTR amyloidosis) (4). Timely identification of the type of amyloid has implications for treatment, genetic counseling, and overall prognosis (5, 6).
When noninvasive evaluation is nondiagnostic, invasive hemodynamic assessment with cardiac catheterization may be pursued. Hemodynamic assessment typically reveals elevated diastolic filling pressures with rapid early diastolic filling and equalization of ventricular diastolic pressures, producing the characteristic “square root” sign. Pulmonary hypertension is common due to chronically elevated left-sided filling pressures. In contrast to constrictive pericarditis, ventricular interdependence and respiratory variation in intracardiac pressures are minimal in RCM.
Endomyocardial biopsy remains the gold standard for definitive diagnosis in select cases and can identify specific pathologic processes, including myocardial fibrosis, infiltrative disorders (eg, amyloid cardiomyopathy, iron overload), eosinophilic infiltration in hypereosinophilic syndromes, noncaseating granulomas in sarcoidosis, or inclusions in the vascular endothelial cytoplasm in Fabry disease (2). Coronary angiography is typically normal unless concomitant coronary artery disease is present (2, 3).
Laboratory evaluation should be directed toward identifying systemic causes and may include iron studies, serum and urine protein electrophoresis with immunofixation, serum free light chains, and complete blood count to assess for eosinophilia. Biopsy of extracardiac tissues may be appropriate when systemic involvement is suspected. Genetic testing is recommended in patients with transthyretin cardiac amyloidosis and may be considered for those with unexplained RCM even in the absence of a known family history, given the potential for inherited forms and implications for screening and counseling (7).
Diagnosis references
1. Gowda SN, Ali HJ, Hussain I. Overview of Restrictive Cardiomyopathies. Methodist Debakey Cardiovasc J. 2022;18(2):4-16. doi:10.14797/mdcvj.1078
2. Pereira NL, Grogan M, Dec GW. Spectrum of Restrictive and Infiltrative Cardiomyopathies: Part 1 of a 2-Part Series. J Am Coll Cardiol. 2018;71(10):1130-1148. doi:10.1016/j.jacc.2018.01.016
3. Rapezzi C, Aimo A, Barison A, et al. Restrictive cardiomyopathy: definition and diagnosis. Eur Heart J. 2022;43(45):4679-4693. doi:10.1093/eurheartj/ehac543
4. Writing Committee, Kittleson MM, Ruberg FL, et al. 2023 ACC Expert Consensus Decision Pathway on Comprehensive Multidisciplinary Care for the Patient With Cardiac Amyloidosis: A Report of the American College of Cardiology Solution Set Oversight Committee. J Am Coll Cardiol. 2023;81(11):1076-1126. doi:10.1016/j.jacc.2022.11.022
5. Bokhari S, Castaño A, Pozniakoff T, et al. (99m)Tc-pyrophosphate scintigraphy for differentiating light-chain cardiac amyloidosis from the transthyretin-related familial and senile cardiac amyloidoses. Circ Cardiovasc Imaging. 2013;6(2):195-201. doi: 10.1161/CIRCIMAGING.112.000132
6. Ruberg FL, Maurer MS. Cardiac Amyloidosis Due to Transthyretin Protein: A Review. JAMA. 2024;331(9):778-791. doi:10.1001/jama.2024.0442
7. Wilde AAM, Semsarian C, Márquez MF, et al. European Heart Rhythm Association (EHRA)/Heart Rhythm Society (HRS)/Asia Pacific Heart Rhythm Society (APHRS)/Latin American Heart Rhythm Society (LAHRS) Expert Consensus Statement on the state of genetic testing for cardiac diseases. J Arrhythm. 2022;38(4):491-553. doi:10.1002/joa3.12717
Treatment of Restrictive Cardiomyopathy
Treat the underlying cause
Diuretics for congestion
Anticoagulation for patients with atrial fibrillation, atrial flutter, or intracardiac thrombi
Management of restrictive cardiomyopathy (RCM) is directed toward treatment of the underlying etiology, relief of congestive symptoms, and prevention of thromboembolic and arrhythmic complications. Early identification of disease-specific causes is critical, as targeted therapies may significantly improve outcomes. Examples include immunosuppressive therapy for cardiac sarcoidosis, iron chelation for iron overload cardiomyopathy, enzyme replacement for Fabry disease, and disease-modifying therapies for cardiac amyloidosis (1, 2, 3).
Volume management with diuretics is the cornerstone of symptomatic treatment for congestion; however, diuretics must be used cautiously because patients with RCM are highly preload dependent, and excessive diuresis may result in reduced cardiac output and hypotension. Guideline-directed medical therapy for heart failure with preserved ejection fraction includes a sodium-glucose cotransporter-2 inhibitor for all patients, as well as mineralocorticoid receptor antagonists and angiotensin-renin system inhibition for select groups (4, 5, 6). However, afterload reducing agents (eg, nitrates, inhibitors of the renin-angiotensin-aldosterone system, neprilysin inhibitors) may be poorly tolerated due to hypotension. The general treatment of chronic heart failure with preserved ejection fraction is discussed in more detail elsewhere.
Atrial fibrillation is frequently poorly tolerated due to the loss of atrial contraction and its contribution to ventricular filling. Accordingly, a rhythm control strategy with antiarrhythmic drugs or ablation is generally preferred, although long-term maintenance of sinus rhythm may be challenging (7). For rate control, low-dose beta-blockers or nondihydropyridine calcium channel blockers may be considered, but these medications should be used with caution given their negative inotropic and chronotropic effects. Bradyarrhythmias and advanced conduction system disease may necessitate permanent pacemaker implantation. Anticoagulation is indicated in patients with atrial fibrillation or flutter, as well as in those with documented intracardiac thrombus.
In advanced cases, cardiac transplantation may be considered in carefully selected patients, provided that severe, irreversible pulmonary hypertension and other end-organ dysfunction (eg, chronic kidney disease, hepatic cirrhosis) are absent. The relatively small LV cavity size and concomitant RV dysfunction may preclude durable left ventricular assist device (LVAD) implantation (1, 8).
Treatment references
1.Muchtar E, Blauwet LA, Gertz MA. Restrictive cardiomyopathy: Genetics, pathogenesis, clinical manifestations, diagnosis, and therapy. Circ Res. 2017;121(7):819–837. doi: 10.1161/CIRCRESAHA.117.310982
2. Pereira NL, Grogan M, Dec GW. Spectrum of Restrictive and Infiltrative Cardiomyopathies: Part 1 of a 2-Part Series. J Am Coll Cardiol. 2018;71(10):1130-1148. doi:10.1016/j.jacc.2018.01.016
3. Pereira NL, Grogan M, Dec GW. Spectrum of Restrictive and Infiltrative Cardiomyopathies: Part 2 of a 2-Part Series. J Am Coll Cardiol. 2018;71(10):1149-1166. doi:10.1016/j.jacc.2018.01.017
4. Heidenreich PA, Bozkurt B, Aguilar D, et al. 2022 AHA/ACC/HFSA Guideline for the Management of Heart Failure: A Report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines. Circulation. 2022;145(18):e895-e1032. doi:10.1161/CIR.0000000000001063
5. Kittleson MM, Panjrath GS, Amancherla K, et al. 2023 ACC Expert Consensus Decision Pathway on Management of Heart Failure With Preserved Ejection Fraction: A Report of the American College of Cardiology Solution Set Oversight Committee. J Am Coll Cardiol. 2023;81(18):1835-1878. doi:10.1016/j.jacc.2023.03.393
6. McDonagh TA, Metra M, Adamo M, et al. 2021 ESC Guidelines for the diagnosis and treatment of acute and chronic heart failure. Eur Heart J. 2021;42(36):3599-3726. doi:10.1093/eurheartj/ehab368
7. Rapezzi C, Aimo A, Barison A, et al. Restrictive cardiomyopathy: definition and diagnosis. Eur Heart J. 2022;43(45):4679-4693. doi:10.1093/eurheartj/ehac543
8. Peura JL, Colvin-Adams M, Francis GS, et al. Recommendations for the use of mechanical circulatory support: device strategies and patient selection: a scientific statement from the American Heart Association. Circulation. 2012;126(22):2648-2667. doi:10.1161/CIR.0b013e3182769a54
Prognosis for Restrictive Cardiomyopathy
The prognosis of RCM is largely determined by the underlying etiology. In idiopathic RCM, prognosis is generally poor (see table ). One study reported a 5-year transplant-free survival of 64% in 94 patients with idiopathic restrictive cardiomyopathy at a wide range of ages, compared with 85% expected survival for the same patient group without RCM (1).
For many patients, no definitive disease-modifying therapy is available, and management is primarily supportive, focusing on symptom control and treatment of complications. Overall, the clinical course is often marked by gradual progression to advanced heart failure, although the rate of deterioration varies depending on the underlying disease process. Patients with advanced disease should be considered for advanced therapies, including heart transplantation.
Prognosis reference
1. Ammash NM, Seward JB, Bailey KR, Edwards WD, Tajik AJ. Clinical profile and outcome of idiopathic restrictive cardiomyopathy. Circulation. 2000;101(21):2490-2496. doi:10.1161/01.cir.101.21.2490
Key Points
In restrictive cardiomyopathy, endocardial thickening or myocardial infiltration leads to a rigid, noncompliant ventricle and diastolic dysfunction; systolic function is typically preserved until late in the disease.
Involvement of valvular structures or the conduction system causes valvular regurgitation, heart block, and arrhythmias.
Etiology is frequently idiopathic; however, a subset of cases is attributable to potentially treatable systemic disorders, including amyloidosis, iron overload cardiomyopathy, and sarcoidosis, highlighting the importance of identifying an underlying cause.
Diagnosis is established with echocardiography, often supplemented by cardiac MRI and targeted evaluation for specific etiologies.
Therapeutic options are often limited and focus on management of the underlying condition when possible. Diuretics may provide symptomatic relief of congestion but must be administered cautiously to avoid excessive reduction in preload.
Some conventional heart failure therapies are used, although inhibitors of the renin-angiotensin-aldosterone system, neprilysin inhibitors, and mineralocorticoid receptor antagonists may cause hypotension and be poorly tolerated in patients with RCM. Cardiac transplantation may be considered in carefully selected patients with advanced disease.
Drug Information for the Topic




