


Scrub typhus is a zoonotic disease caused by Orientia tsutsugamushi; mites are the reservoir and vector and transmit infection to various hosts, including rodents, other small animals, and humans. Symptoms are fever, a primary lesion, a macular rash, and lymphadenopathy. Diagnosis is by serology, polymerase chain reaction testing, and immunohistochemistry. Treatment is with doxycycline.


Zoonotic diseases are infections that can be naturally transmitted between animals and humans.
These diseases are caused by a variety of organisms, including bacteria, viruses, fungi, and parasites.
Some zoonotic diseases, such as rabies and cowpox, are transmitted directly from animals to people through contact with saliva, blood, urine, or feces. Others may spread through the air or through bites and scratches. In other diseases, transmission occurs through the bite of insects such as mosquitoes, ticks or fleas.
In Lyme disease, for example, deer ticks transmit the bacteria from infected carrier animals, such as mice, to humans or other animals. Insects that carry and transmit germs that cause diseases in people are called vectors.
Other zoonotic diseases, like Salmonella infection, are contracted by consuming food, water, or milk that has been contaminated by an infected animal, by consuming food that has been washed or grown in contaminated water, or by eating undercooked meat from an animal with Salmonella.
Zoonotic diseases make up more than half of all emerging infectious diseases (those that are rapidly increasing in incidence worldwide).
Zoonotic diseases not only cause illness and death in people, but also impact animal health, leading to illness in pets, zoo animals, wild animals and livestock, and reduced food availability. These diseases can have devastating effects on economies because of trade restrictions, health care expenditures, and negative effects on tourism.
Rabies is a viral zoonotic disease that is primarily spread through the bites or scratches of animals that are infected, called reservoirs. Common animal reservoirs for rabies include bats, skunks, raccoons, and foxes. Rabies spreads to the brain and spinal cord and can be fatal if not treated promptly.
Anthrax is a bacterial zoonotic disease commonly found in animals exposed to food, air, or water that is contaminated with anthrax spores. These spores can live in the environment and infect both people and animals when they are ingested, inhaled, or absorbed through open wounds. Humans may become infected through contact with infected animals or animal products that are contaminated with spores. Once inside the body, the spores develop into bacteria. The bacteria release toxins that can cause inflammation, bleeding, tissue death, and potentially sepsis.
Lyme disease is a bacterial zoonotic disease that is spread when a deer tick bites an infected carrier animal, such as a mouse, and ingests the bacteria that causes Lyme disease. The tick then bites animals or people, spreading the bacteria to them. Symptoms include fever, headache, fatigue, and a distinctive bull’s eye-shaped rash. If untreated, Lyme disease can affect the joints, heart, and nervous system.
The best way to prevent zoonotic disease is to limit your exposure to infected animals and vectors.
When contact with infected animals is necessary, it is important that you wear protective clothing and equipment like hats, gloves and glasses to avoid bites and scratches, and that you wash your hands thoroughly after handling animals.
To protect against insect vectors such as mosquitoes, ticks, and fleas, you can wear long pants and long-sleeve clothing, use mosquito netting, use insect repellents, and check for ticks after being outside in areas where they live.
It is also important to handle food safely and to avoid food that might be contaminated.
To protect animal health, keep healthy animals separate from infected animals and also protect them from exposure to insect vectors and contaminated food sources.
Copyright © 2026 Merck & Co., Inc., Rahway, NJ, USA and its affiliates. All rights reserved.
Scrub typhus is a zoonosis related to rickettsial diseases.
O. tsutsugamushi is transmitted by the bites of trombiculid mite larvae (chiggers), which are the primary natural reservoir and vector. Chiggers feed on forest and rural rodents, including rats, voles, and field mice, but these animals are considered secondary (or maintaining) hosts (1). Similarly, human infection can occur after a chigger bite. Humans are accidental dead-end hosts. Human contact with infected animals cannot directly transmit infection.


PDC/SCIENCE PHOTO LIBRARY
Risk factors for scrub typhus include agricultural work, exposure to certain types of vegetation, outdoor activities in rural areas, and proximity to rodents or other farm animals (2).
Historically, scrub typhus was considered to be endemic across South Asia, East Asia, and Southeast Asia (the Tsutsugamushi triangle), with over 1 billion people at risk. Incidence is an estimated 1 million clinical cases annually (3). The identification of cases from the Arabian Peninsula, Chile, and Kenya suggests a wider global distribution in regions with warmer climates (4).
Scrub typhus is rare in the United States and is not a nationally notifiable disease (5).
General references
1. Weitzel T, Dittrich S, López J, et al. Endemic Scrub Typhus in South America. N Engl J Med. 2016;375(10):954-961. doi:10.1056/NEJMoa1603657
2. Wang Q, Ma T, Ding F, et al. Global and regional seroprevalence, incidence, mortality of, and risk factors for scrub typhus: A systematic review and meta-analysis. Int J Infect Dis. 2024;146:107151. doi:10.1016/j.ijid.2024.107151
3. Xu G, Walker DH, Jupiter D, Melby PC, Arcari CM. A review of the global epidemiology of scrub typhus. PLoS Negl Trop Dis. 2017;11(11):e0006062. Published 2017 Nov 3. doi:10.1371/journal.pntd.0006062
4. Bonell A, Lubell Y, Newton PN, Crump JA, Paris DH. Estimating the burden of scrub typhus: A systematic review. PLoS Negl Trop Dis. 2017;11(9):e0005838. Published 2017 Sep 25. doi:10.1371/journal.pntd.0005838
5. CDC. Information for Public Health Officials. December 11, 2025. Accessed January 9, 2026.
Symptoms and Signs of Scrub Typhus
After an incubation period of approximately ≥ 7 days (symptoms usually occur within 7 to 10 days and last 14 to 21 days) (1), symptoms of scrub typhus start suddenly and include fever, chills, headache, and generalized lymphadenopathy.

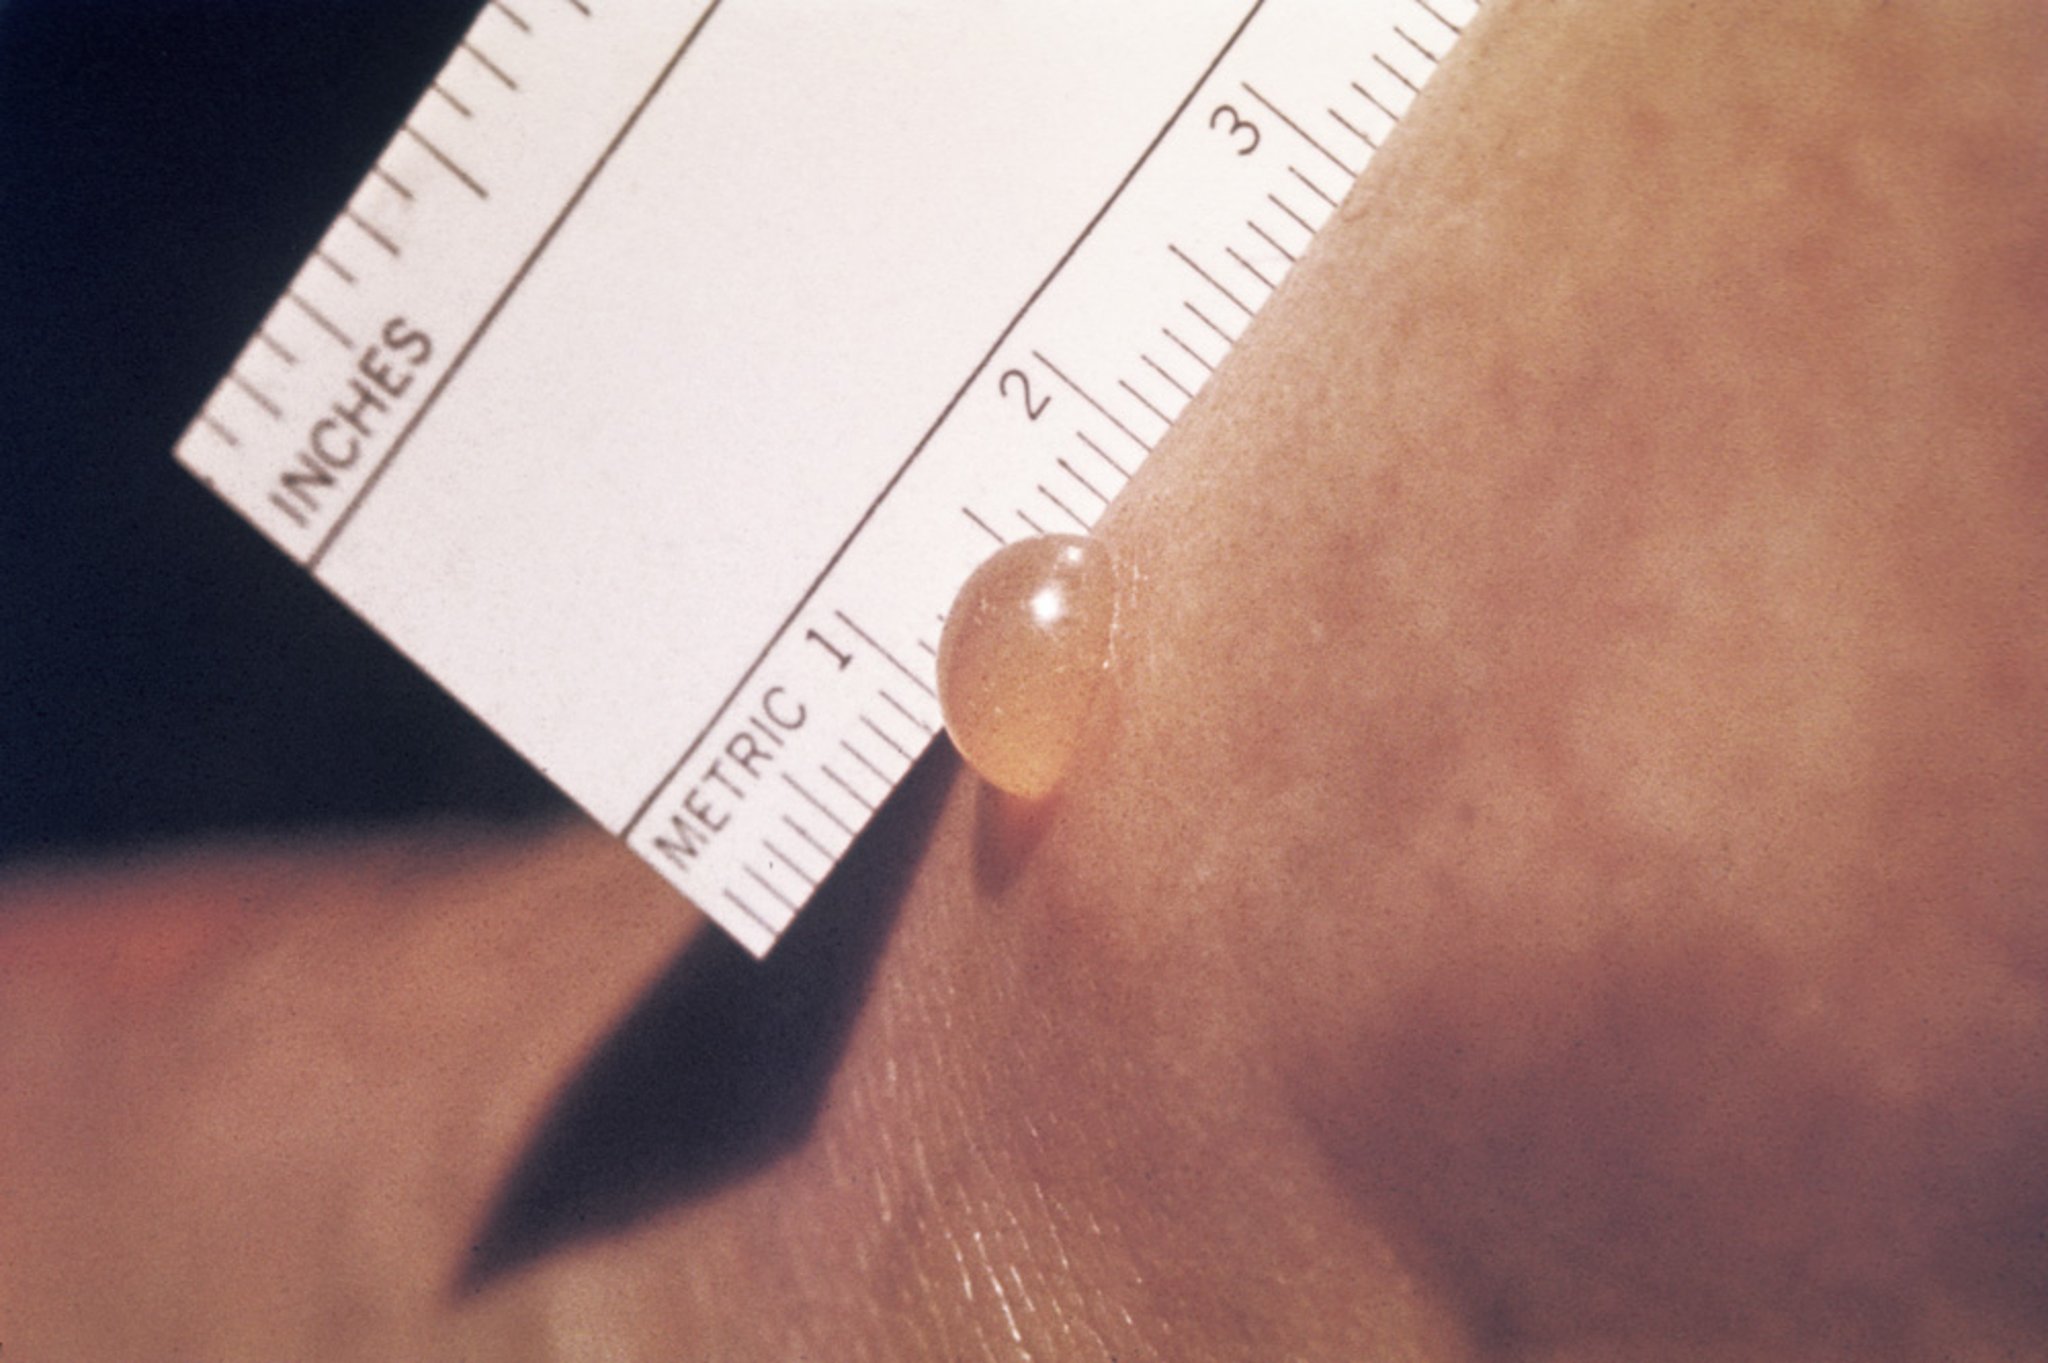
This photo shows a person's skin 24 hours after being bitten by a chigger (mite larvae). Note the vesicle at the bite site was caused by the bite of a larval harvest mite of the genus Trombicula.
CDC
At the onset of fever, an eschar often develops at the site of the chigger bite. The typical lesion begins as an erythematous, indurated lesion about 1 cm in diameter; it eventually vesiculates, ruptures, and becomes covered with a black scab. Whether different strains of O. tsutsugamushi can cause an eschar varies, and an eschar is easier to detect in people with light skin. A macular rash develops on the trunk during days 5 to 8 of fever in 25 to 50% of patients, often extending to the arms and legs (1). It may disappear rapidly or become maculopapular and intensely colored. Regional lymph nodes enlarge.


This photo shows a scrub typhus eschar on a person's leg.
DR P. MARAZZI/SCIENCE PHOTO LIBRARY
Fever rises during the first week, often to 40 to 40.5° C. Headache is severe and common, as is conjunctival injection. Cough is present during the first week of fever, and pneumonitis may develop during the second week.
In severe cases, pulse rate increases; blood pressure drops; and delirium, stupor, and muscular twitching develop. Splenomegaly may be present, and interstitial myocarditis is more common than in other rickettsial diseases. In untreated patients, high fever may persist ≥ 2 weeks, then falls gradually over several days. With therapy, defervescence usually begins within 36 hours. Recovery is prompt and uneventful.

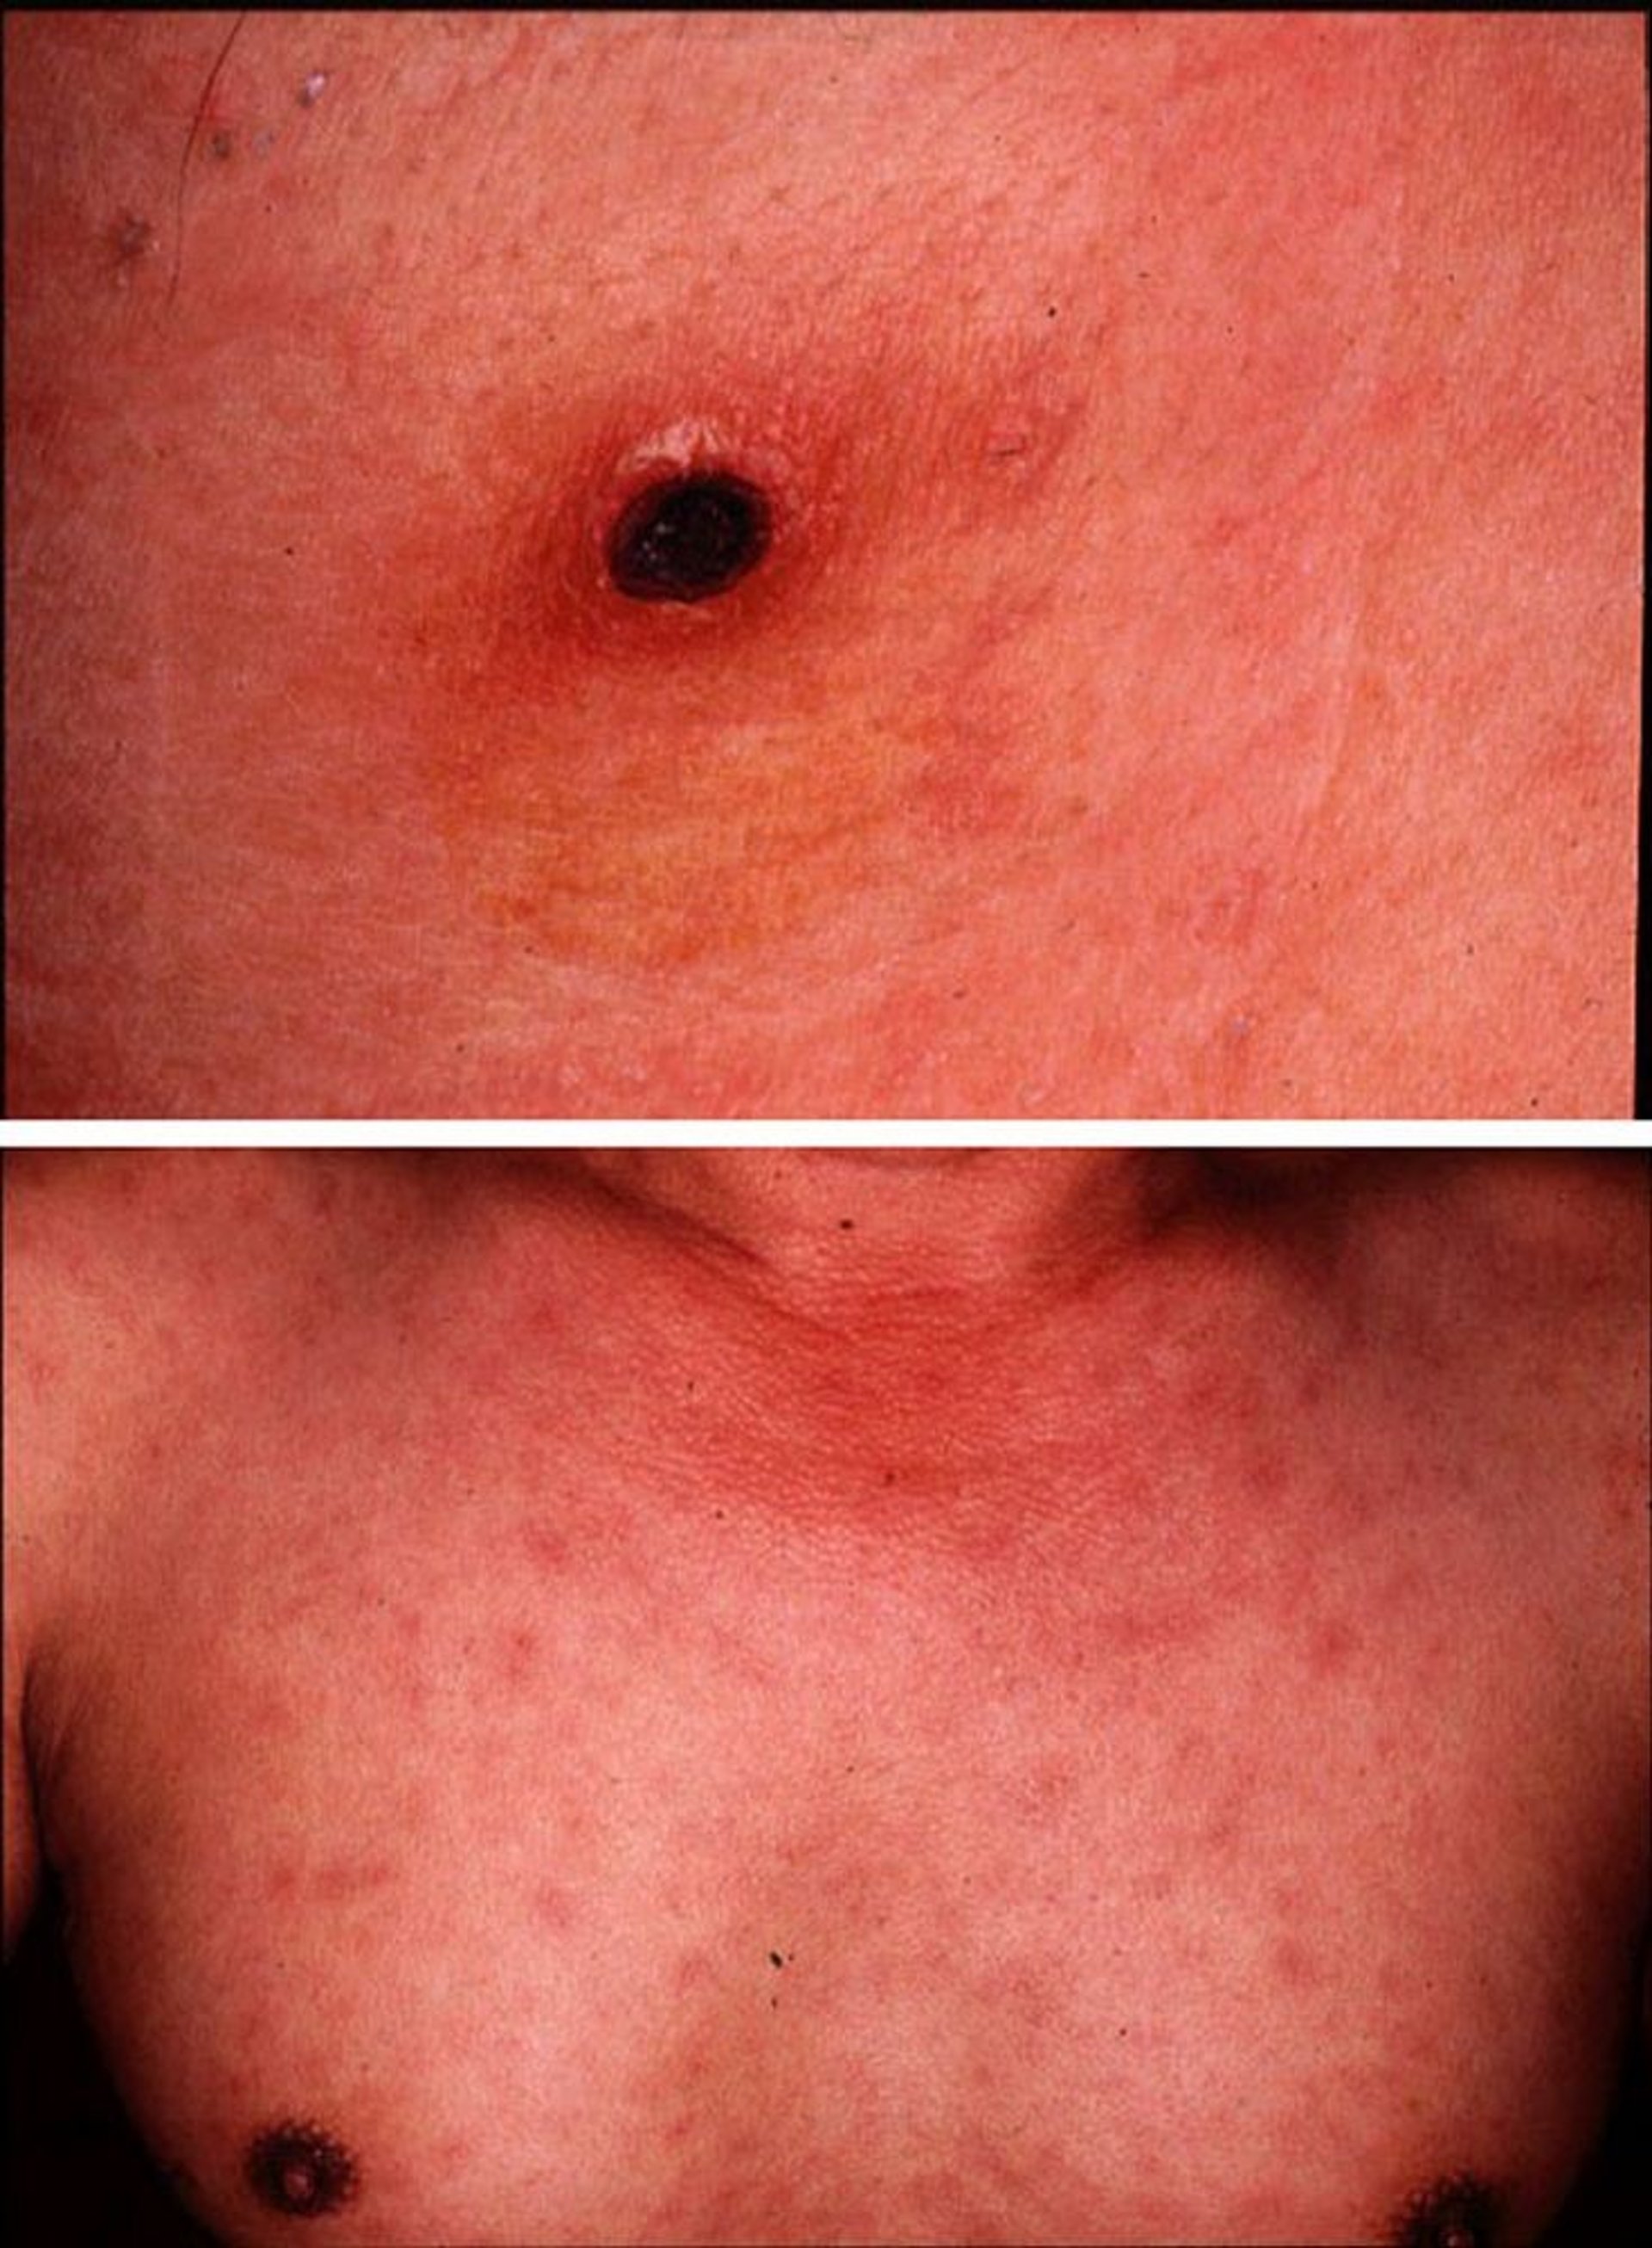
Scrub typhus (tsutsugamushi disease) manifests as an eschar at the site of a chigger bite (top). A diffuse macular rash follows the appearance of the eschar (bottom).
Images courtesy of Yoshiki Taniguchi, MD. From Taniguchi, Y: Eschar, fever, and rash in a 43-year-old man. Dermatology Online Journal 3(2), 1997.
Symptoms and signs reference
1. CDC. Clinical Overview of Scrub Typhus. May 15, 2024. Accessed January 9, 2026.
Diagnosis of Scrub Typhus
History and physical examination
Molecular diagnostic testing (polymerase chain reaction [PCR]) of infected tissue or blood specimens
Biopsy of tissue with immunohistochemistry to detect organisms
Acute and convalescent serologic testing (serologic testing not useful acutely)
The diagnosis of scrub typhus relies on timely identification of clinical signs such as fever, rash, and eschar with satellite lymphadenopathy in the appropriate epidemiologic context. Manifestations of scrub typhus are similar to those of Rocky Mountain spotted fever and epidemic typhus. However, scrub typhus usually occurs in different geographic areas.
Laboratory confirmation is primarily through indirect immunofluorescence assay serology showing increased titers between acute and convalescent samples (1). Weil-Felix OX-K agglutination assays are not recommended because of low sensitivity and specificity (1).
PCR testing on skin biopsies or an eschar swab may allow earlier diagnosis, and immunohistochemistry on formalin-fixed tissue biopsy is an adjunctive method.
Because scrub typhus is not common in the United States, serologic and molecular assays are not typically available at regional health departments but may be performed at the United States Centers for Disease Control and Prevention (CDC).
For further details, see Diagnosis of Rickettsial and Related Infections.
Diagnosis reference
1. CDC. Clinical Overview of Scrub Typhus. May 15, 2024. Accessed January 9, 2026.
Treatment of Scrub Typhus
Doxycycline
Sometimes other tetracyclines or azithromycin
Antibiotics are most effective if given soon after symptoms begin.
Doxycycline is the first-line treatment of scrub typhus. This medication is administered until the patient improves, has been afebrile for 48 hours, and has received treatment for at least 7 days.
For patients who are pregnant or who have severe doxycycline allergy, azithromycin has been shown to be a safe and effective alternative to doxycycline (1).
In patients who are not pregnant, azithromycin and other tetracyclines may be alternatives to doxycycline; however, the certainty of evidence is low (2).
Chloramphenicol is also an alternative treatment. Chloramphenicol can cause adverse hematologic effects, which require monitoring of blood indices, and, in neonates, gray baby syndrome.
Although some tetracyclines can cause tooth staining in children < 8 years of age, the United States Centers for Disease Control and Prevention (CDC) advises that a course of doxycycline is warranted (3), given for 5 days for mild illness and for 10 days for high-risk children. Research indicates that short courses of doxycycline (5 to 10 days, as used for rickettsial disease) can be used in children without causing tooth staining or weakening of tooth enamel (4).
Treatment references
1. Lee SC, Cheng YJ, Lin CH, et al. Comparative effectiveness of azithromycin for treating scrub typhus: A PRISMA-compliant systematic review and meta-analysis. Medicine (Baltimore). 2017;96(36):e7992. doi:10.1097/MD.0000000000007992
2. El Sayed I, Liu Q, Wee I, Hine P. Antibiotics for treating scrub typhus. Cochrane Database Syst Rev. 2018;9(9):CD002150. Published 2018 Sep 24. doi:10.1002/14651858.CD002150.pub2
3. CDC. Clinical Overview of Scrub Typhus. May 15, 2024. Accessed January 9, 2026.
4. CDC. Research: Doxycycline and Tooth Staining. May 15, 2024. Accessed January 2, 2026.
Prevention of Scrub Typhus
Eliminating or decreasing mite populations by clearing brush and spraying infested areas with residual insecticides helps prevent scrub typhus.
Insect repellents (eg, diethyltoluamide [DEET], picaridin, IR3535, oil of Lemon eucalyptus (OLE), para-menthane-diol (PMD), or 2-undecanone) should be used on skin surfaces when exposure is likely.
Key Points
Scrub typhus is transmitted by the bites of mite larvae (chiggers).
Fever (often accompanied by an eschar at the bite site), chills, severe headache, and generalized lymphadenopathy start suddenly; a rash develops and spreads.
Diagnosis is by serology, PCR testing, and immunohistochemistry.
Treatment is with doxycycline, which results in rapid improvement even in severe cases; azithromycin is an alternative in pregnant patients or in patients with doxycycline allergy.
Drug Information for the Topic




